




Here's how it works
01. Edit your ky medicaid prior authorization form online
Type text, add images, blackout confidential details, add comments, highlights and more.
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send kentucky medicaid prior authorization form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Kentucky Prior with our platform

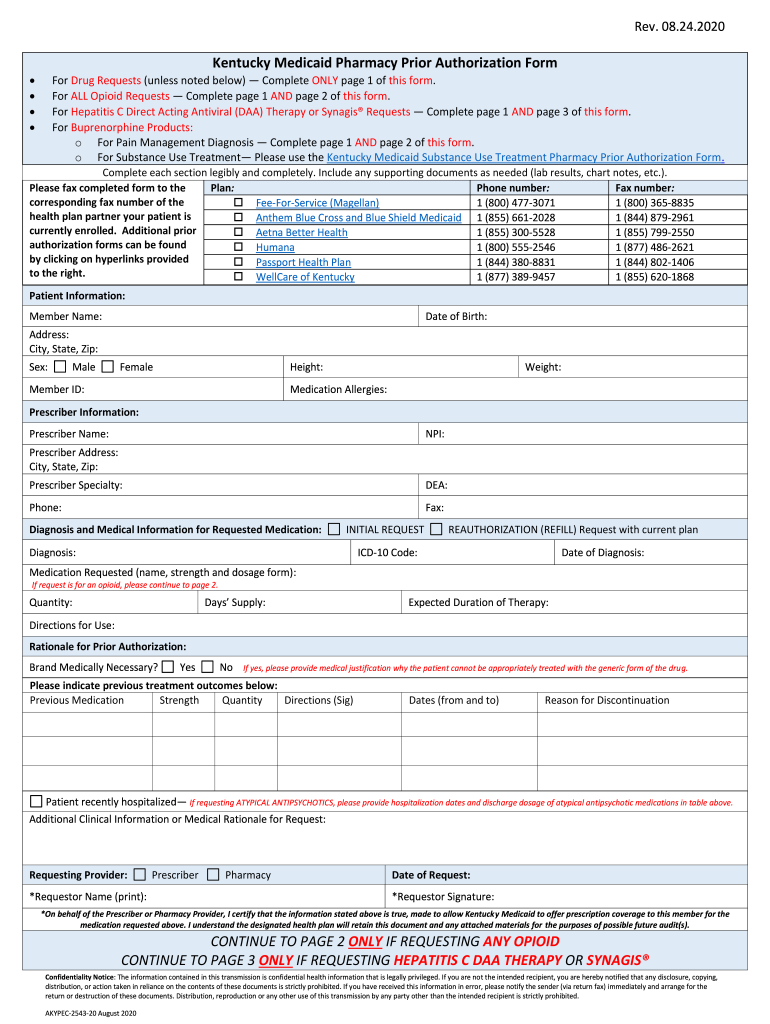
- Click ‘Get Form’ to open the Kentucky Medicaid Pharmacy Prior Authorization Form in the editor.
- Begin by filling out the Patient Information section. Include the member's name, date of birth, address, and sex. Ensure all fields are completed legibly.
- Next, provide Prescriber Information. Enter the prescriber's name, NPI, address, specialty, and contact details accurately.
- In the Diagnosis and Medical Information section, specify whether this is an initial request or a reauthorization. Fill in the diagnosis and ICD-10 code as required.
- Complete the Medication Requested field with details about the medication including name, strength, dosage form, quantity, and expected duration of therapy.
- If applicable, continue to page 2 for opioid requests or page 3 for Hepatitis C DAA therapy requests. Follow prompts for additional information as needed.
- Review all entries for accuracy before submitting. Attach any necessary supporting documents like lab results if required.
Start using our platform today to streamline your document editing and submission process for free!
Fill out kentucky prior online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Co Marketing Agreement Template
The Co-Marketing Agreement outlines the collaboration between Company A and Company B for joint marketing efforts aimed ...

Exhibition Loan Agreement Template
The Exhibition Loan Agreement is a legally binding document that outlines the terms and conditions for the loan of speci ...

Model Agency Contract Template
The Model Agency Contract Agreement outlines the terms and conditions under which a modeling agency represents a model. ...

Salon Booth Rental Lease Agreement Template
The Salon Booth Rental Lease Agreement outlines the terms and conditions for renting a booth space in a salon. It define ...

Nurse Practitioner Employment Contract Template
The Nurse Practitioner Employment Agreement outlines the terms of employment between an Employer and a licensed Nurse Pr ...

Hairdress Contract Template
The document is a Hairdresser Services Agreement that outlines the terms and conditions between a Service Provider and a ...

Company Confidentiality Agreement Template
This Confidentiality Agreement outlines the terms under which confidential information is shared between a Disclosing Pa ...

LLC Contribution Agreement Template
The Limited Liability Company Contribution Agreement outlines the terms under which members of a limited liability compa ...