




Here's how it works
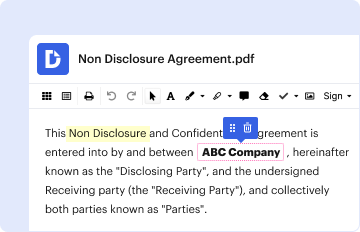
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
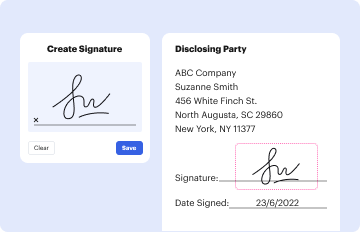
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
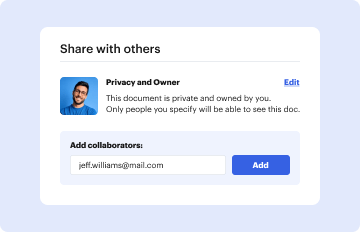
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out physician additional with our platform

- Click ‘Get Form’ to open the physician additional form in the editor.
- Begin by filling out the identifying information section. Enter the Board Claim Number, Employee's Last Name, First Name, M.I., Date of Injury, and SSN or Board Tracking Number.
- In section A, provide details about the County of Injury and the name and address of your counsel if represented.
- Move to section B to identify the currently authorized treating physician. Fill in their name and address.
- Indicate whether you are requesting a Change of Physician or Additional Treatment by completing section C. Specify the names and addresses of the new physicians as needed.
- In section D, certify the existence of a valid fee contract if applicable.
- Finally, complete section E by certifying that all parties have been notified and sign with your details including date and contact information.
Start using our platform today for free to streamline your document editing and submission process!
Fill out physician additional online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


