




Here's how it works
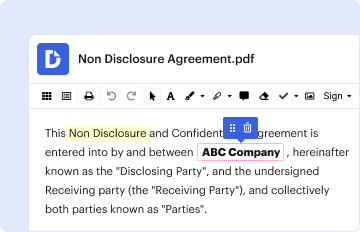
01. Edit your 4102888150 online
Type text, add images, blackout confidential details, add comments, highlights and more.
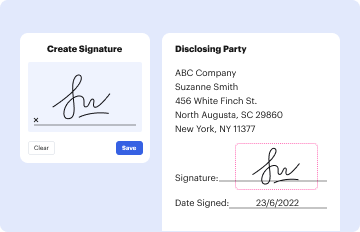
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
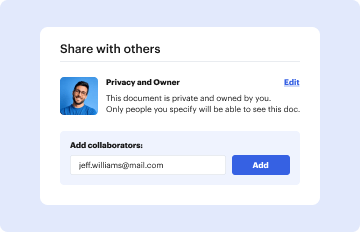
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out 4102888150 with our platform

- Click ‘Get Form’ to open it in the editor.
- Begin by entering the patient’s name in the designated field, ensuring you format it as 'Last, First'.
- Fill in the patient's address, including the zip code, followed by their primary and secondary insurance details.
- Provide the contact phone number and date of birth for accurate identification.
- Complete the policy number fields for both primary and secondary insurances.
- Indicate the patient's height and weight, along with any relevant diagnosis information.
- Check appropriate boxes to prescribe necessary equipment or supplies. If you need to delete any supply, indicate it clearly and initial next to it.
- Ensure all prescriptions are filled out correctly, specifying settings and durations where applicable.
- Finally, have the prescribing physician sign and date the form before submission for payment consideration.
Start using our platform today to streamline your document editing and form completion process for free!
Fill out 4102888150 online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


