




Here's how it works
01. Edit your oncology referral form online
Type text, add images, blackout confidential details, add comments, highlights and more.
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send broome oncology portal via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out HEMATOLOGY ONCOLOGY PATIENT REFERRAL FORM with our platform

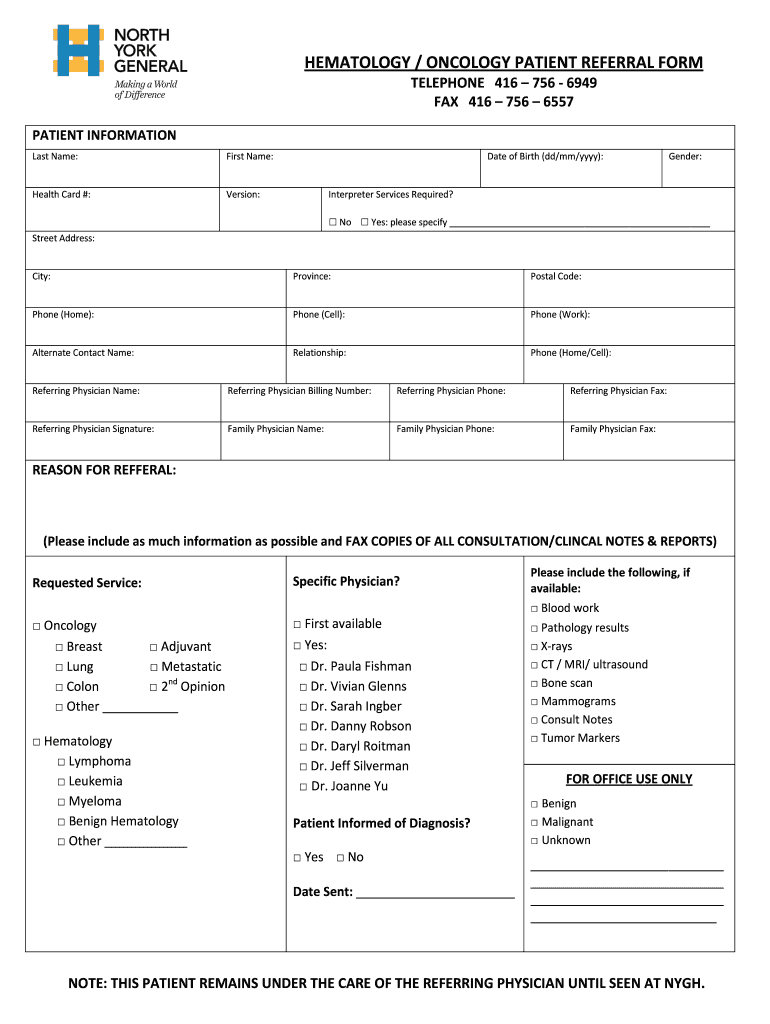
- Click ‘Get Form’ to open the HEMATOLOGY ONCOLOGY PATIENT REFERRAL FORM in the editor.
- Begin by entering the patient information. Fill in the last name, first name, health card number, version, date of birth, and gender. If interpreter services are required, indicate this by checking 'Yes' and specifying the language needed.
- Complete the address section with the patient's street address, city, province, postal code, and phone numbers (home, cell, work). Also provide an alternate contact's name and relationship to the patient.
- Input details for the referring physician including their name, billing number, phone number, fax number, and signature. Repeat this for the family physician.
- In the 'Reason for Referral' section, provide detailed information about why the referral is necessary. Select requested services and specific physicians if applicable.
- Indicate whether the patient has been informed of their diagnosis and include any relevant medical documents such as blood work or imaging results.
Start using our platform today to streamline your document editing and form completion process for free!
Fill out HEMATOLOGY ONCOLOGY PATIENT REFERRAL FORM online
It's free
It's free
See more HEMATOLOGY ONCOLOGY PATIENT REFERRAL FORM versions
We've got more versions of the HEMATOLOGY ONCOLOGY PATIENT REFERRAL FORM form. Select the right HEMATOLOGY ONCOLOGY PATIENT REFERRAL FORM version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


