


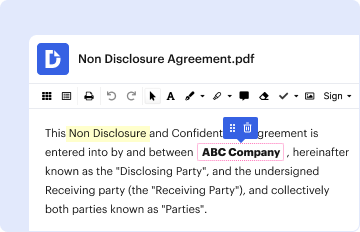
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.


Type text, add images, blackout confidential details, add comments, highlights and more.
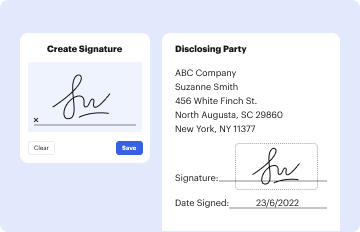
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
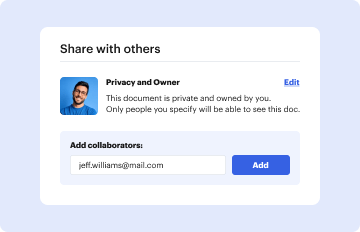
Send it via email, link, or fax. You can also download it, export it or print it out.
The Eagles Landing Family Practice new patient forms collect essential information from new patients to ensure seamless integration into the healthcare system. These forms typically include personal details, medical history, insurance information, and consent to practice policies. By filling out these forms, patients establish a foundational relationship with the healthcare provider, allowing efficient and effective medical service delivery.
Completing these forms accurately and thoroughly can expedite the check-in process during the first visit.
Securing the necessary forms can generally be accomplished through several convenient channels:
These forms serve several critical functions that benefit both the new patient and the healthcare provider:
These forms are specifically designed for new patients registering at the Eagles Landing Family Practice. They are essential for:

These forms comply with legal and regulatory standards to protect both the patient’s privacy and the practice’s operational procedures.
Eagle's Landing Family Practice typically offers several submission options to cater to different patient preferences.
These diverse submission methods provide flexibility and convenience for patients completing their new patient registration forms.
We've got more versions of the eagles landing family practice new patient forms form. Select the right eagles landing family practice new patient forms version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2002 | 4.8 Satisfied (58 Votes) |
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
After you log in to the PyraMED Student Patient Portal, find the tab called My Forms and click on it. Please complete any forms that you find here. Contact
Please send a copy of my medical record(s) to my new physician, Dr (First Name) (Last Name). Dr. (Last Name)s address is: street address, city, state zip code.Read more


