




Here's how it works
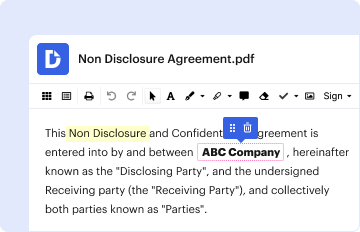
01. Edit your 816 257 3256 online
Type text, add images, blackout confidential details, add comments, highlights and more.
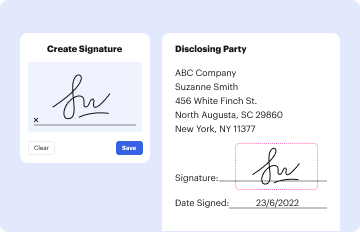
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
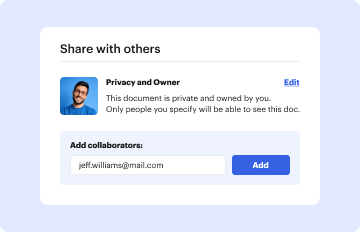
03. Share your form with others
Send user access request form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out the PCIP Appeal Form with Our Platform

- Click ‘Get Form’ to open the PCIP Appeal Form in the editor.
- Begin by entering the patient’s name and Plan ID number in the designated fields. Ensure accuracy as this information is crucial for processing your appeal.
- Fill in the claim number(s) related to your appeal. This helps identify the specific claim under review.
- Provide your name and select your status from the options: Covered person, Patient, or Authorized representative. If you are an authorized representative, briefly explain your relationship to the patient.
- Complete your mailing address, phone number, and email address. This ensures that PCIP can contact you regarding your appeal.
- Indicate how you prefer to receive a response—either by letter or email.
- In the provided space, clearly explain why you believe the initial decision was incorrect, referencing specific benefit provisions from your plan brochure.
- If necessary, attach additional sheets or supporting documents such as medical records or letters from physicians that substantiate your appeal.
- Finally, confirm that all information is correct by signing and dating the form before submission.
Start using our platform today to easily complete and submit your PCIP Appeal Form for free!
Fill out pcip form online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


