




Here's how it works
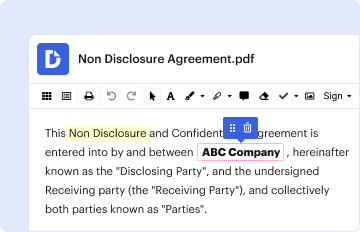
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
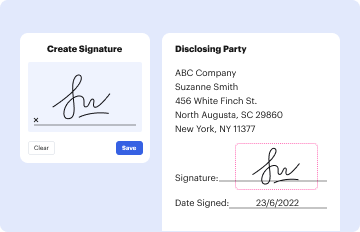
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
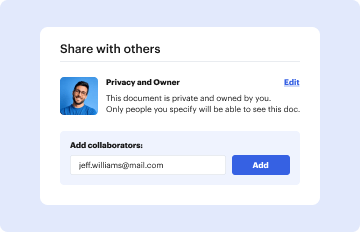
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out ePayment Enrollment Authorization Form - Providers - Select Health of South Carolina ePayment Enroll with our platform

- Click ‘Get Form’ to open it in the editor.
- Begin by completing the EFT Authorization Form. Ensure you provide an original signature and include a government-issued ID on your legal entity's letterhead.
- Fill in the contact information for your financial institution, including the name, address, and phone number. Attach a bank authorization letter or a voided check.
- On page 2, provide mandatory Provider Contact Information 1 & 2. These are essential for any inquiries regarding EFT/ERA information.
- Indicate if you wish to enroll for all TIN & NPI EFT Payers as specified on pages 5 & 6. If applicable, list individual payers starting from page 7.
- Once completed, sign and email your form as a PDF attachment to EFTEnrollment@changehealthcare.com or fax it to 615.238.9615.
Start using our platform today to streamline your ePayment Enrollment process effortlessly!
Fill out ePayment Enrollment Authorization Form - Providers - Select Health of South Carolina ePayment Enroll online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


