cms 1763 Preview on Page 1

Cms 1763-2026

Here's how it works

  • 01. Edit your cms 1763 online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
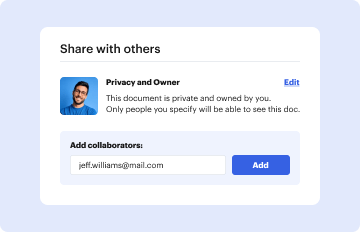
  • 03. Share your form with others

    Send form cms 1763 via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out cms 1763 with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by entering the 'Name of Enrollee' and 'Medicare Number' in the designated fields. Ensure that all information is accurate to avoid processing delays.
  3. If someone other than the enrollee is executing this request, fill in their name in the 'Name of Person' field.
  4. Indicate the specific type of insurance you wish to terminate by checking the appropriate boxes for 'Supplementary Medical Insurance' and/or 'Hospital Insurance'.
  5. Provide the dates when each type of insurance will end. This is crucial for proper documentation.
  6. In the section for reasons, briefly state your reason for termination if desired, although it is not mandatory.
  7. Sign the form in ink. If signed by mark (X), ensure two witnesses sign below with their full addresses.
  8. Complete your mailing address and telephone number before submitting the form.

Start using our platform today to easily fill out your cms 1763 form online for free!

See more cms 1763 versions

We've got more versions of the cms 1763 form. Select the right cms 1763 version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20224.6 Satisfied (40 Votes)
20174.8 Satisfied (86 Votes)
20064.4 Satisfied (545 Votes)
19974.4 Satisfied (40 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

How to fill out Form CMS 1763? Name of Enrollee. Medicare Number. Name of the Person, if Other than Enrollee, Who Is Executing the Request (if appropriate). This is a Request for Termination of Hospital Insurance/Medical Insurance. Date Hospital Insurance Will End. Reasons for the termination request.
Use this form: If you have premium Part A or Part B, but wish to no longer be enrolled. If you have Part B, but recently re-joined the workforce with access to employer-sponsored health insurance and wish to voluntarily terminate this coverage.
Do you have to pay for Medicare? Yes, most people pay $185 per month for Medicare Part B and may pay more if they choose extra coverage options. Part A is free if you worked for 10 years or more.
CMS 1763. Form Title. Request for Termination of Premium Hospital Insurance of Supplementary Medical Insurance.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

be ready to get more

Complete this form in 5 minutes or less

cms 1763 form

IBM Virtual Machine Facility/370 Quick Guide for Users

The Using. CMS section of this. Quick Reference Guide. Using the VM/370 System. 9. Page 11. describes how you can use a CMS virtual machine under VM/370.

Learn more
Supporting Statement for the CMS-1763 Request for

May 15, 2009 The CMS-1763 is completed by an SSA claims or field representative using information provided by the Medicare enrollee during an interview. The

Learn more
Statement by the Association of American Medical

Jun 10, 2020 The Resident Physician Shortage Reduction Act (H.R. 1763/S. 348) would take a step toward addressing the physician shortage by gradually and

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here