




Here's how it works
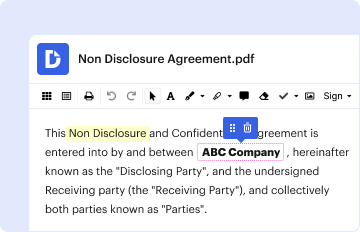
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
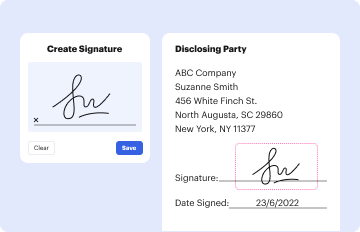
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
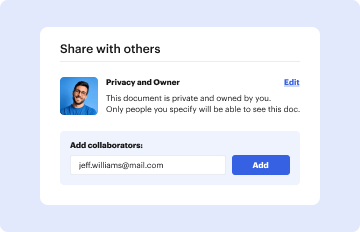
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out PAYMENT ADJUSTMENT YEAR 2019 MEDICARE EHR INCENTIVE PROGRAM CRITICAL ACCESS HOSPITAL RECONSIDERATION

- Click ‘Get Form’ to open it in the editor.
- Begin with SECTION 1: HOSPITAL INFORMATION. Fill in the required fields marked with an asterisk, including the Legal Hospital Name, CMS Certification Number, and Hospital Address. Ensure accuracy as this information is crucial for processing.
- Proceed to SECTION 2: PAYMENT ADJUSTMENT RECONSIDERATION. Indicate whether the hospital has previously demonstrated meaningful use by selecting 'Yes' or 'No'. Then, choose at least one reason for reconsideration from the provided options.
- In SECTION 3: CERTIFICATION STATEMENT CONFIRMATION, read through the certification notice carefully. Confirm your understanding by typing your name and date in the designated fields to validate your submission.
- Once completed, save your application and attach it to an email addressed to qnetsupport@hcqis.org. Remember to retain a copy for your records before sending.
Start using our platform today to streamline your form completion process for free!
Fill out PAYMENT ADJUSTMENT YEAR 2019 MEDICARE EHR INCENTIVE PROGRAM CRITICAL ACCESS HOSPITAL RECONSIDERATION online
It's free
It's free
See more PAYMENT ADJUSTMENT YEAR 2019 MEDICARE EHR INCENTIVE PROGRAM CRITICAL ACCESS HOSPITAL RECONSIDERATION versions
We've got more versions of the PAYMENT ADJUSTMENT YEAR 2019 MEDICARE EHR INCENTIVE PROGRAM CRITICAL ACCESS HOSPITAL RECONSIDERATION form. Select the right PAYMENT ADJUSTMENT YEAR 2019 MEDICARE EHR INCENTIVE PROGRAM CRITICAL ACCESS HOSPITAL RECONSIDERATION version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2019 | 4.8 Satisfied (86 Votes) |
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more




