




Here's how it works
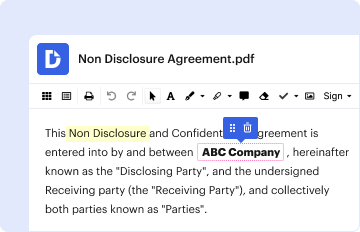
01. Edit your arkansas medicaid referral form online
Type text, add images, blackout confidential details, add comments, highlights and more.
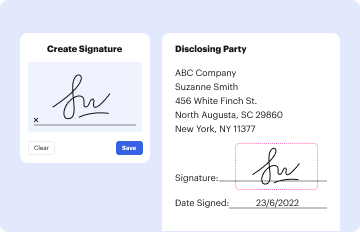
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send medicaid referral form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out the referral form with our platform

- Click ‘Get Form’ to open the referral form in the editor.
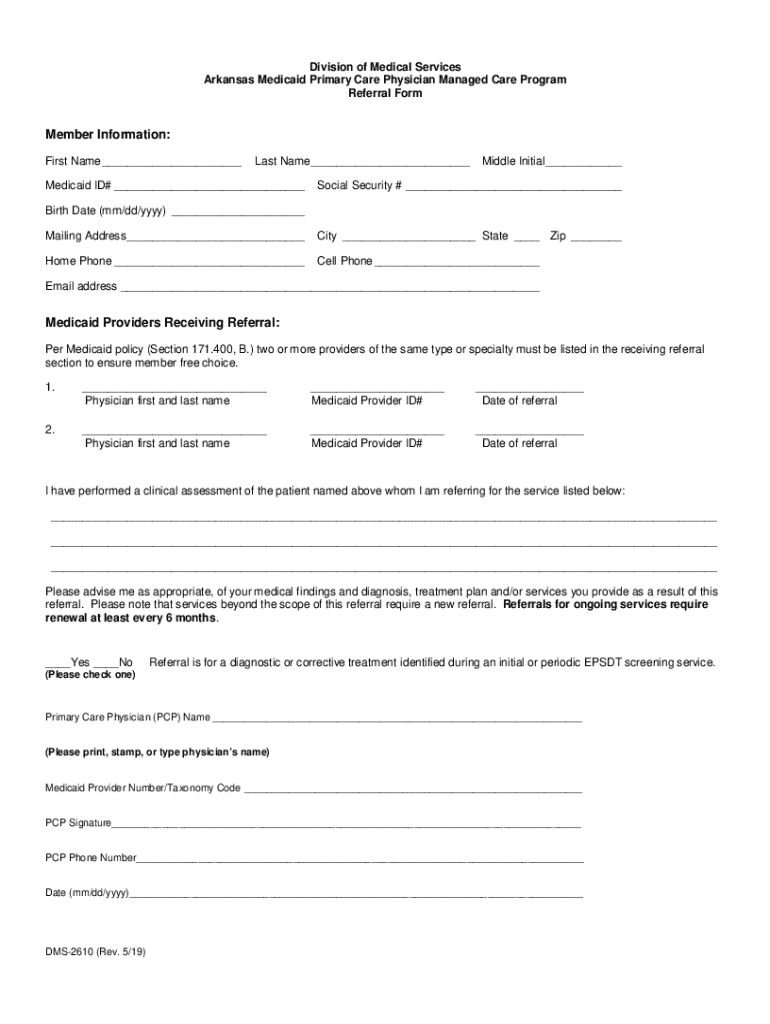
- Begin by filling out the Member Information section. Enter the first name, last name, Medicaid ID number, middle initial, social security number, birth date, mailing address, city, state, zip code, home phone, cell phone, and email address.
- In the Medicaid Providers Receiving Referral section, list at least two providers of the same type or specialty. For each provider, enter their first and last name, Medicaid Provider ID number, and the date of referral.
- Provide a detailed clinical assessment of the patient in the designated area. Ensure you include any relevant medical findings and treatment plans.
- Indicate whether the referral is for diagnostic or corrective treatment by checking 'Yes' or 'No'.
- Complete the Primary Care Physician (PCP) Name section by printing or typing your name along with your Medicaid Provider Number/Taxonomy Code.
- Sign and date the form in the appropriate fields before submitting it.
Start using our platform today to easily complete your referral form online for free!
Fill out referral form online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


