




Here's how it works
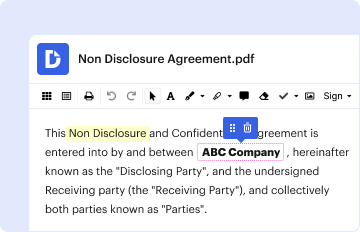
01. Edit your durable medical equipment authorization request online
Type text, add images, blackout confidential details, add comments, highlights and more.
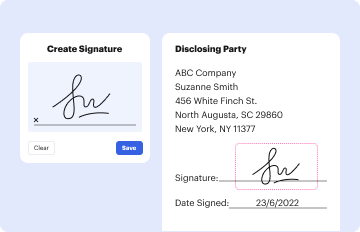
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
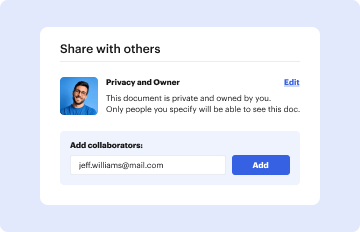
03. Share your form with others
Send authorization request dme form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out authorization request dme form with our platform

- Click ‘Get Form’ to open the authorization request dme form in the editor.
- Begin with Part A: Requestor Information. Select whether this is an Initial Request or Correction, and fill in the required fields such as Date Requested and Requested By.
- Move to Part B: Claimant Information. Enter the Claimant's Case ID, Date of Birth, First Name, Last Name, and Date of Injury accurately.
- Proceed to Part C: Provider Information. Input the OWCP Provider ID, Tax ID, Provider Name, and Fax Number. Indicate if you are providing care for a family member.
- In Part D: Service Line Information, specify the body part being treated and enter up to four Diagnosis Codes. Fill in service dates and select appropriate procedure codes.
- Finally, attach all necessary Supporting Documents in Part E before submitting your completed form through our platform.
Start using our platform today for free to streamline your document editing and submission process!
Fill out authorization request dme form online
It's free
It's free
See more authorization request dme form versions
We've got more versions of the authorization request dme form form. Select the right authorization request dme form version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Councilmembers: Hatfield, present; Peone, present; Ward, present
The document contains the minutes from the City Council meeting of Hauser, Idaho, held on July 14, 2010. Key topics disc ...

Municipal Community Redevelopment Agencies - Miami-Dade County
The document is a resolution from the Southeast Overtown/Park West Community Redevelopment Agency authorizing the issuan ...

Gerald Silverman, Board Member
The document contains the meeting minutes of the Civil Service Board of Miami, held on April 6, 2010. It details the pro ...

Mallon, present Hatfield, present Lefebvre, present
The document contains the minutes from the City Council meeting of Hauser, Idaho, held on January 11, 2012. It includes ...

Transfer Duty Guide - Sars
The Transfer Duty Guide provides a comprehensive overview of the Transfer Duty Act 40 of 1949, detailing the application ...

LONDON JOINT
The document outlines the agenda for the Inner North East London Joint Overview & Scrutiny Committee meeting held on Feb ...

Community by Community Approach - Lake County Health
The document outlines the community health assessment process conducted by the Lake County Health Department, emphasizin ...

Federal Home Loan Bank Review
The document is the November 1942 issue of the Federal Home Loan Bank Review, which discusses various aspects of housing ...


