


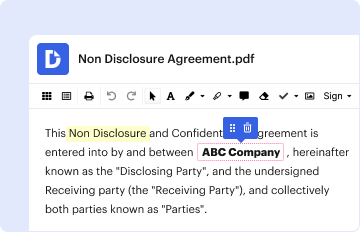
01. Edit your medical assessment forms online
Type text, add images, blackout confidential details, add comments, highlights and more.


Type text, add images, blackout confidential details, add comments, highlights and more.
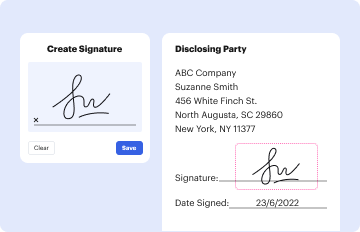
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
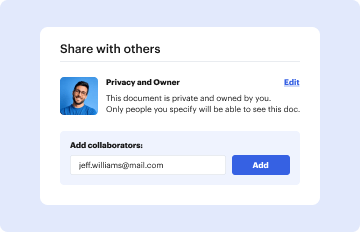
Send form pa 635 via email, link, or fax. You can also download it, export it or print it out.

Start using our platform today for free to streamline your medical assessment form completion!
We've got more versions of the medical assessment forms form. Select the right medical assessment forms version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2016 | 4.8 Satisfied (161 Votes) |
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
PATIENT ASSESSMENT FORM (new patients only). Patient Information. HGT. WGT. SS#. Name (Last, First, MI). DOB. Gender. Male Female. Home Phone. Cell Phone.Read more
For a product problem: Describe the problem (quality, performance, or safety concern) in sufficient detail so that the circumstances surrounding the defect orRead more
This form is provided as a courtesy to prospective residents/residents and licensees. (Please attach separate pages if needed.) I. FACILITY INFORMATION (ToRead more


