




Here's how it works
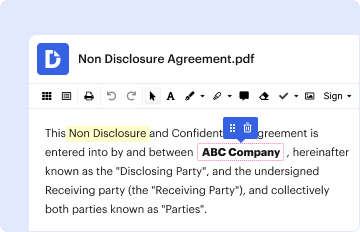
01. Edit your masshealth medical release form online
Type text, add images, blackout confidential details, add comments, highlights and more.
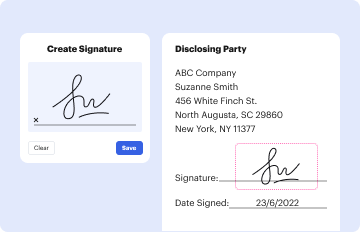
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
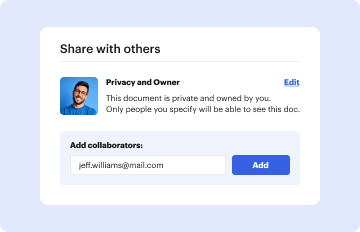
03. Share your form with others
Send masshealth privacy office via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out ma madsmr masshealth with our platform

- Click ‘Get Form’ to open the ma madsmr masshealth in the editor.
- Begin by filling out Section I, where you grant permission for your health-care provider to share medical information. Clearly print the name of the applicant or member.
- In Section II, provide the details of your health-care provider, including their name, address, and phone number. Ensure all information is accurate to avoid delays.
- Move to Section III and specify what medical information can be shared. Check any boxes that apply regarding sensitive information like AIDS/HIV status or drug/alcohol use.
- In Section IV, review the privacy notice and understand that this permission lasts for six months unless canceled in writing.
- Complete Section V by signing and dating the form. If someone else is filling it out on behalf of the applicant/member, ensure they provide their authority details.
Start using our platform today to fill out your ma madsmr masshealth form online for free!
Fill out ma madsmr masshealth online
It's free
It's free
See more ma madsmr masshealth versions
We've got more versions of the ma madsmr masshealth form. Select the right ma madsmr masshealth version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


