




Here's how it works
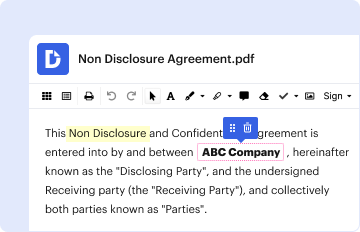
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
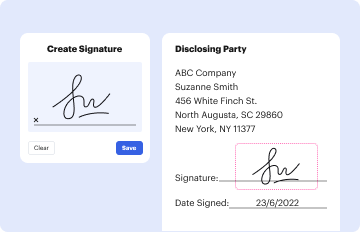
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out first choice claim form with our platform

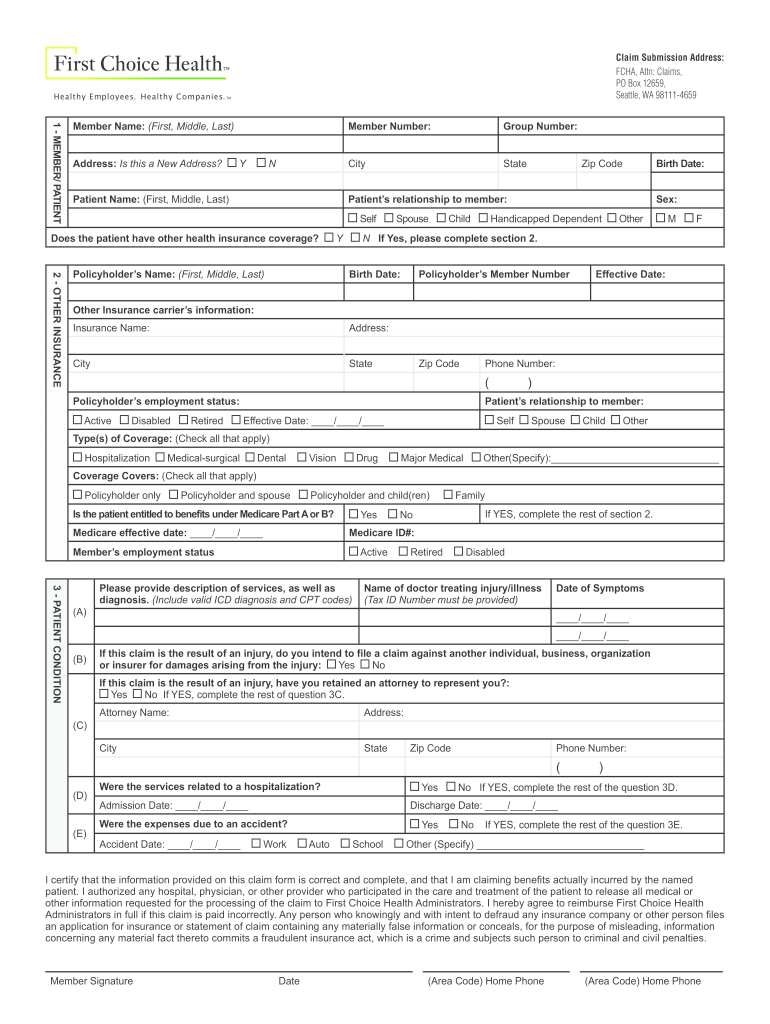
- Click ‘Get Form’ to open the first choice claim form in the editor.
- Begin by filling out the MEMBER/PATIENT section. Enter the member's name, address, and indicate if this is a new address. Provide the patient's name, member number, group number, birth date, and relationship to the member.
- If applicable, complete the OTHER INSURANCE section. Fill in the policyholder’s details and insurance carrier information. Indicate the type of coverage and whether the patient has Medicare benefits.
- In the PATIENT CONDITION section, describe services provided along with diagnosis codes. If related to an injury, answer questions regarding claims against other parties and attorney representation.
- Finally, review all entered information for accuracy. Sign and date at the bottom of the form to certify correctness before submission.
Start using our platform today for free to streamline your claim submission process!
Fill out first choice claim form online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


