Alohacare credentialing email form - alohacare Preview on Page 1

Alohacare credentialing email form - alohacare 2026

Here's how it works

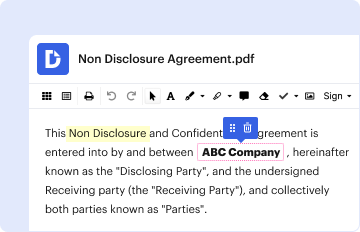
  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

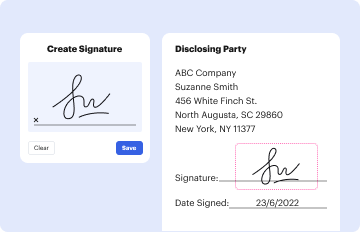
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
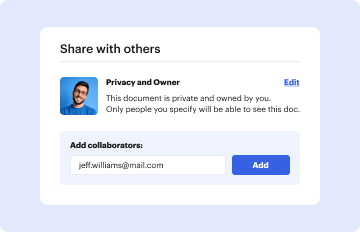
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out Alohacare credentialing email form - alohacare with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the Alohacare credentialing email form in the editor.
  2. Begin by filling out the Identification and Demographics section. Enter your last name, first name, middle name, and any previous surnames. Ensure you provide your Social Security Number and Date of Birth accurately.
  3. In the Provider Classification section, select your provider type from the options provided (e.g., MD, DO, etc.) and indicate your gender.
  4. Complete the Professional IDs section by entering your National Provider Identification Number, Medicare Number, and Medicaid details as applicable.
  5. Fill in the Office Information sections for both primary location and mailing address. Include practice name, address, phone number, and email where indicated.
  6. Proceed to State Licensure and list all licenses held in the past five years along with their details including expiration dates.
  7. Continue through sections on Board Certification/Specialty, Education, Training, Professional Liability Insurance, Hospital Affiliations, Professional Practice History, Questionnaire, and finally Attestation/Consent & Release Form. Ensure all fields are completed accurately.

Start using our platform today to streamline your document editing experience for free!

See more Alohacare credentialing email form - alohacare versions

We've got more versions of the Alohacare credentialing email form - alohacare form. Select the right Alohacare credentialing email form - alohacare version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20244.3 Satisfied (20 Votes)
20174.3 Satisfied (43 Votes)
20094.5 Satisfied (32 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

If you have questions, call us at AlohaCare Customer Service at 1-877-973-0712 or TTY 1-877-447-5990 or Med-QUEST at 1-800-316-8005 or TTY 711 or 1-800-603-1201.
Refer to the latest version of the AlohaCare Provider Manual for more information on prior authorizations. Please contact AlohaCare Provider Services at 808-973-1650 or toll-free at 1-800-434-1002.
Contact Us You may contact our Provider Relations Call Center at 808-973-1650 or toll-free at 1-800-434-1002 or submit your inquiry via email to providerhelp@alohacare.org if you have any questions.
We specialize in QUEST (Medicaid) health insurance to people living on Oahu, Kauai, Molokai, Lanai, Maui and Hawaii Island. We are mission driven to care for people who are underserved with specific health needs. We provide health care coverage for Hawaiis QUEST (Medicaid) beneficiaries.
Payer Name: Aloha Care|Payer ID: 99030|Professional (CMS1500)/Institutional (UB04)[Hospitals]

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

You can call us at our toll-free phone: 1-866-973-6395 and ask for an expedited appeal. For an after-hours expedited appeals request you can call us at 808-356-5959. If we decide that you do need an expedited appeal, we will make a decision and give you an answer within 72 hours.
1-800-MEDICARE (1-800-633-4227) If you want Medicare to be able to give your personal information to someone other than you, you need to fill out an Authorization to Disclose Personal Health Information. Get this form in Spanish.

Related links

Hawaii QUEST Integration Annual Monitoring Report to

Sep 23, 2019 Hawaiis QUEST Integration (QI) is a Department of Human Services (DHS) expands Medicaid coverage to children and adults provides Medicaid

Learn more
Patient Name

This form is for reference purposes only. identity and credentials of the healthcare provider. This form is for reference purposes only. licensing and

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here