w10 form Preview on Page 1

W10 form hospital 2026

Here's how it works

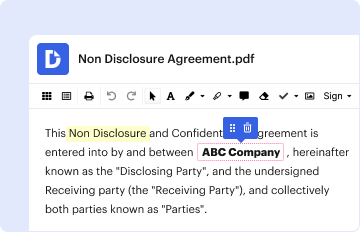
  • 01. Edit your w10 form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

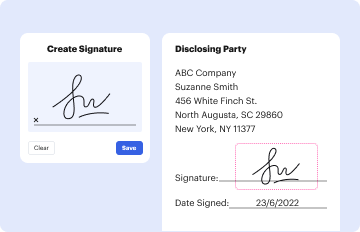
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
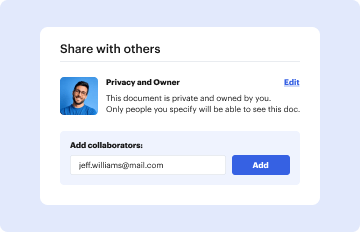
  • 03. Share your form with others

    Send what is a w10 via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out w10 form hospital with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the W10 form hospital in the editor.
  2. Begin by filling out your personal information in the designated fields, including your name, title, and organization. Ensure accuracy for proper identification.
  3. In the comments section, provide your feedback regarding the proposed changes. You can select from options such as 'Agree with proposed changes' or 'Do not agree with proposed changes'.
  4. If you are commenting on behalf of an organization, check the appropriate box and include any additional details required.
  5. Review all entered information for completeness and correctness before submitting.
  6. Once satisfied, submit your comments online or export the completed form for email or fax submission.

Start using our platform today to streamline your document editing and submission process for free!

See more w10 form versions

We've got more versions of the w10 form form. Select the right w10 form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20104.4 Satisfied (34 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

w10 medical form

STATE OF CONNECTICUT

W-10. (Rev 02/23). PREFERRED NAME. (Last, First, Middle). LEGAL NAME. (Last, First, Middle) FOLLOW-UP BY (Name and Address of Provider or Clinic). 1Read more

Learn more
Health Assessment Initial Pre-Placement Form - Duke HR

The purpose of this evaluation is to screen for immunity to communicable diseases and to identify physical, mental, or emotional impairments

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here