




Here's how it works
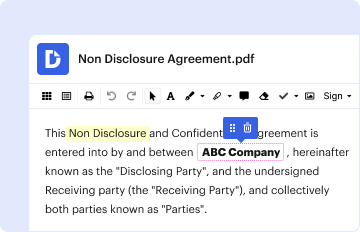
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
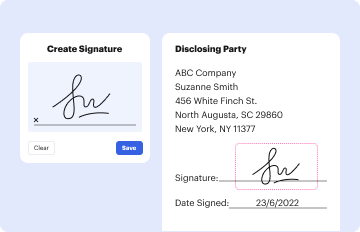
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out TREATMENT OR TESTING BY AUTHORIZED MEDICAL PROVIDER WC-205 with our platform

- Click ‘Get Form’ to open it in the editor.
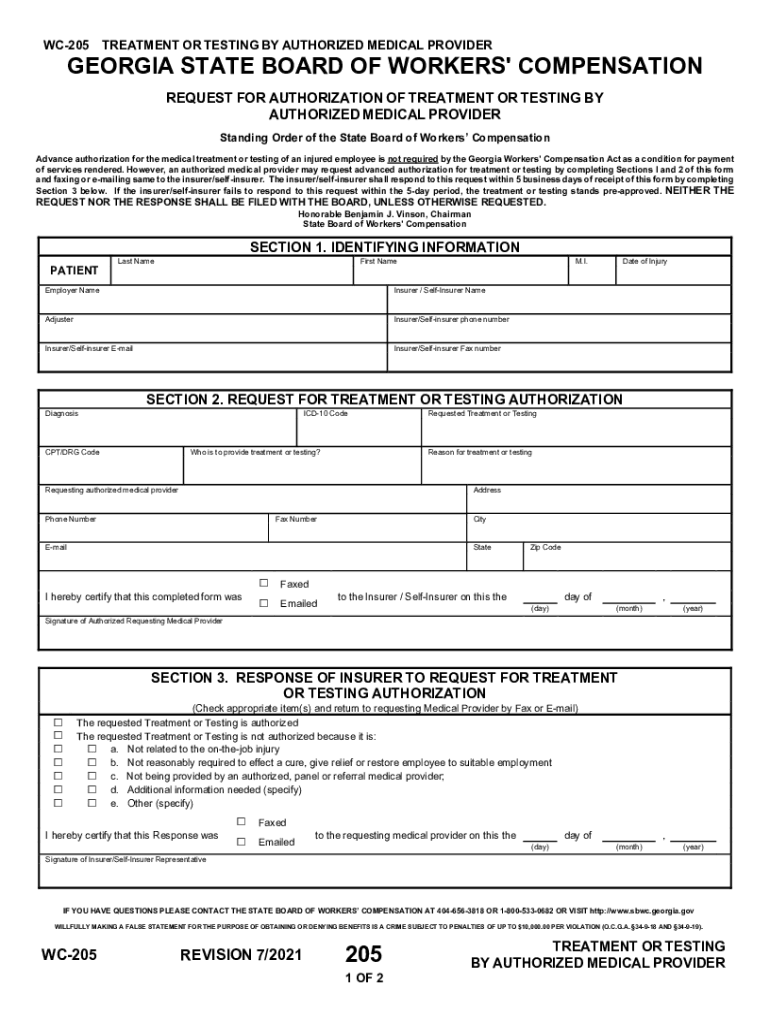
- Begin by filling out Section 1, which includes identifying information such as the patient's last name, first name, employer name, and diagnosis. Ensure all fields are completed accurately.
- Proceed to Section 2 to request treatment or testing authorization. Enter the ICD-10 and CPT/DRG codes, specify who will provide the treatment, and detail the requested treatment or testing along with the reason for it.
- In this section, also include your contact information as the requesting authorized medical provider. Make sure to certify that you have faxed or emailed this form to the insurer/self-insurer.
- Finally, review Section 3 where the insurer will respond. This section is not for you to fill out but is crucial for understanding how your request will be processed.
Start using our platform today for free to streamline your document editing and form completion!
Fill out TREATMENT OR TESTING BY AUTHORIZED MEDICAL PROVIDER WC-205 online
It's free
It's free
See more TREATMENT OR TESTING BY AUTHORIZED MEDICAL PROVIDER WC-205 versions
We've got more versions of the TREATMENT OR TESTING BY AUTHORIZED MEDICAL PROVIDER WC-205 form. Select the right TREATMENT OR TESTING BY AUTHORIZED MEDICAL PROVIDER WC-205 version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more




