




Here's how it works
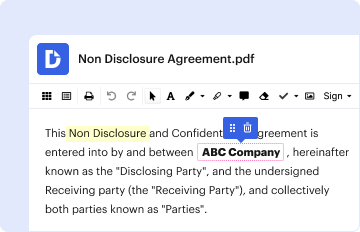
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
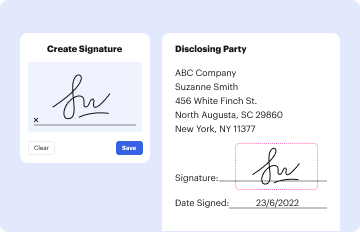
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
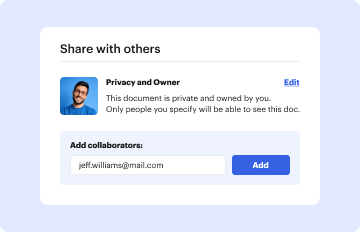
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out GA CVCP Work Release Form with DocHub

- Click ‘Get Form’ to open the GA CVCP Work Release Form in our platform.
- Begin by entering the Claim Number at the top of the form. This is essential for tracking your application.
- Fill in the Patient/Victim's Name and Address accurately to ensure proper identification.
- Provide the Social Security Number (SSN) and Date of Birth (DOB) of the patient/victim for verification purposes.
- Indicate the Date(s) when the patient/victim was under care, specifying both start and end dates.
- Answer whether the patient/victim is permanently disabled and unable to work by selecting 'Yes' or 'No'. If 'No', provide additional dates when they were unable to work due to injuries.
- Describe the condition that made the patient/victim unable to perform work-related activities in detail.
- Ensure both Medical Provider and Patient/Victim sign where indicated, along with their respective dates and contact information.
Start filling out your GA CVCP Work Release Form online for free today using our editor!
Fill out GA CVCP Work Release Form online
It's free
It's free
See more GA CVCP Work Release Form versions
We've got more versions of the GA CVCP Work Release Form form. Select the right GA CVCP Work Release Form version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2016 | 4.8 Satisfied (106 Votes) |
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


