




Here's how it works
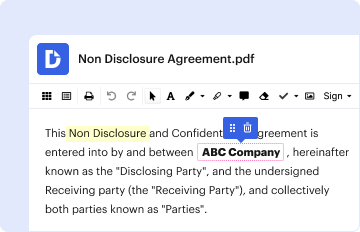
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
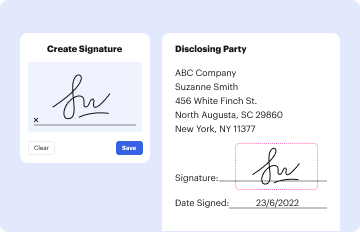
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
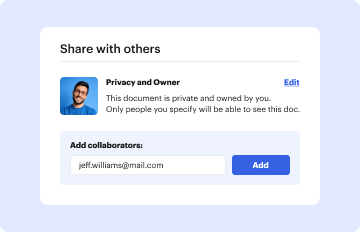
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out STATE BOARD OF PHARMACY 800 SW Jackson, Suite 1414

- Click ‘Get Form’ to open it in the editor.
- Begin by filling in the 'CLOSING FACILITY' section. Enter the facility's name, Kansas registration number, physical address, closure date, city, state, zip code, and county. Indicate whether the facility holds a Retail Dealer Permit.
- Provide details for the 'Person Responsible for Pharmacy Closure', including their phone number.
- In the 'FACILITY RECEIVING PATIENT FILES & RECORDS' section, input the name and registration number of the receiving facility along with their contact information.
- Next, complete the 'FACILITY RECEIVING REMAINING STOCKS OF DRUGS' section with similar details as above.
- Finally, ensure you fill out the 'OWNER CERTIFICATION' section by signing and dating the form. Include your printed name and email address.
Start using our platform today to streamline your document editing and submission process for free!
Fill out STATE BOARD OF PHARMACY 8 00 SW Jackson, Suite 1414 online
It's free
It's free
See more STATE BOARD OF PHARMACY 8 00 SW Jackson, Suite 1414 versions
We've got more versions of the STATE BOARD OF PHARMACY 8 00 SW Jackson, Suite 1414 form. Select the right STATE BOARD OF PHARMACY 8 00 SW Jackson, Suite 1414 version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


