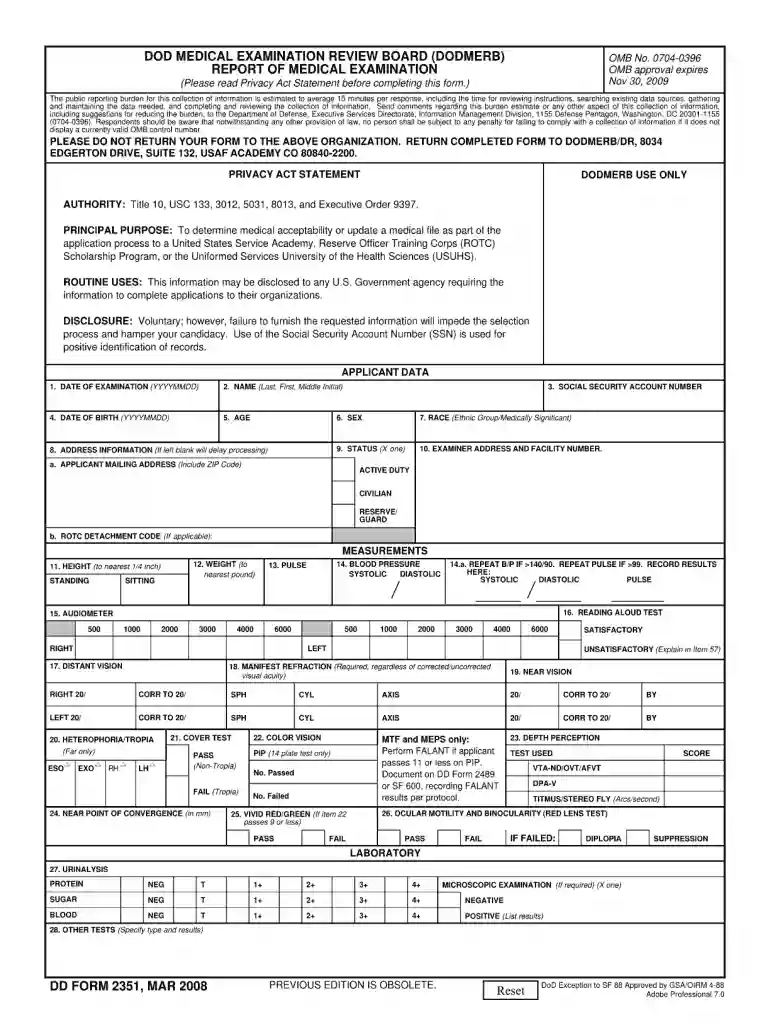
dodmerb Preview on Page 1

Dd form medical 2026

Here's how it works

  • 01. Edit your dodmerb online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send dd form medical via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out dd form medical with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the dd form medical in the editor.
  2. Begin by entering your personal information in the designated fields, including your name, date of birth, and contact details. Ensure accuracy for effective processing.
  3. Proceed to the medical history section. Here, you will need to provide details about any previous conditions or treatments. Use the text boxes provided to elaborate as necessary.
  4. Next, fill out the current medications section. List all medications you are currently taking, including dosages and frequency. This information is crucial for your healthcare provider.
  5. Finally, review all entered information for completeness and accuracy before submitting. Utilize our platform’s editing tools to make any necessary adjustments easily.

Start using our platform today for free to streamline your dd form medical completion!

See more dodmerb versions

We've got more versions of the dodmerb form. Select the right dodmerb version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20084.9 Satisfied (513 Votes)
20044.2 Satisfied (33 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

dd 2351

NEW YORK STATE MEDICAID PROGRAM DURABLE

Jul 19, 2005 Enter the date on which the provider or an authorized representative signed the claim form. The date should be in the format MM/DD/YY. NoteRead more

Learn more
DD Form 2807-2, ACCESSIONS MEDICAL HISTORY

PURPOSE: To obtain medical data for determination of medical fitness for enlistment, induction, appointment, and retention for applicants and members of theRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here