Patient First Name: Middle Initial:Last Name: School grade: Preview on Page 1

Patient First Name: Middle Initial:Last Name: School grade: 2026

Here's how it works

  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

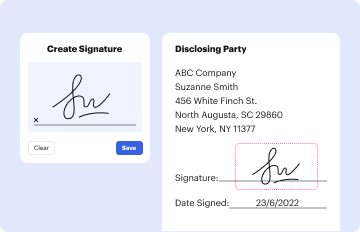
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
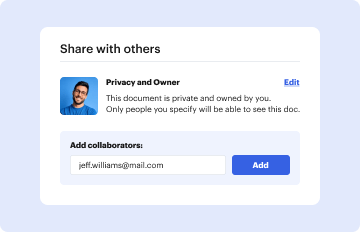
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out Patient First Name: Middle Initial: Last Name: School grade: with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Begin by clicking ‘Get Form’ to open the document in the editor.
  2. Locate the section labeled 'Patient’s Name'. Here, you will find three fields for input: 'First Name', 'Middle Initial', and 'Last Name'.
  3. In the 'First Name' field, enter the patient's first name clearly. Ensure there are no typos for accurate identification.
  4. Next, move to the 'Middle Initial' field. If applicable, input the middle initial of the patient. If there is none, you may leave this field blank.
  5. Finally, fill in the 'Last Name' field with the patient's surname. Double-check for accuracy as this is crucial for record keeping.
  6. After completing these fields, proceed to fill out any additional sections such as 'School Grade' if required.

Start using our platform today to streamline your document editing and form completion process!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Part 80: Rules and Regulations on Controlled Substances in

The prescription shall indicate the name and address of the prescriber, Drug Enforcement Administration registration number, signature of the prescriber, nameRead more

Learn more
PREFERRED NAME CHANGE FORM

(212) 241-6691. All Students (Medical and Graduate) can indicate their preferred first name to the school (First, Middle Initial, Last):

Learn more
Patient Last Name: DOB

Last Name: First Name: Middle Initial: Date of Birth (month, day, year) Education/Highest Grade Completed. High School Graduate/GED. Assessment (with 1st

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here