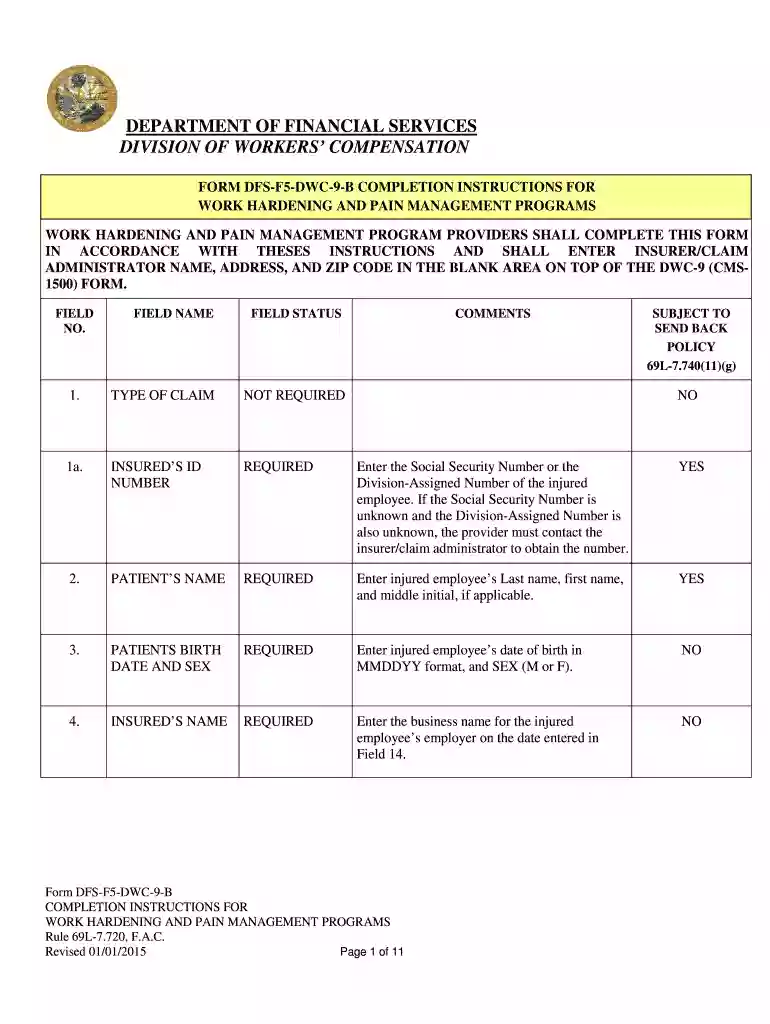
dfs f5 dwc 9 form Preview on Page 1

Dfs f5 dwc 9 form 2026

Here's how it works

  • 01. Edit your dfs f5 dwc 9 form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out dfs f5 dwc 9 form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the dfs f5 dwc 9 form in the editor.
  2. Begin by entering the insurer or claim administrator's name, address, and ZIP code in the designated area at the top of the form.
  3. In Field 1, select the type of claim. For Field 1a, input the insured’s ID number, which is required for processing.
  4. Fill in the patient’s name in Field 2, ensuring to include their last name, first name, and middle initial if applicable.
  5. For Fields 3 and 4, enter the patient's birth date and sex as well as the insured's name (the employer's business name).
  6. Complete Field 5 with the patient's address including street, city, state, and zip code.
  7. In Field 10, indicate if the patient’s condition is related to employment or an accident by marking 'A', 'B', or 'C'.
  8. Finally, ensure all required fields are filled out accurately before submitting your form for processing.

Start using our platform today to fill out your dfs f5 dwc 9 form online for free!

See more dfs f5 dwc 9 form versions

We've got more versions of the dfs f5 dwc 9 form form. Select the right dfs f5 dwc 9 form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20154.8 Satisfied (96 Votes)
20094 Satisfied (25 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

Form DWC 1 is the official form that California businesses and employees use to file a workers compensation claim. The employee fills out a portion of the form, and the employer fills out the remainder. The employer then sends the completed form to their workers comp insurance company in order to file a claim.
The Division of Workers Compensation (DWC) monitors the administration of workers compensation claims, and provides administrative and judicial services to assist in resolving disputes that arise in connection with claims for workers compensation benefits.
Workers Compensation Claim Form (DWC-7) Form DWC-7 is a notice to provide injured workers with rights, benefits and contact information. DOWNLOAD DWC-7 FORM.
What You Shouldnt Tell Your Workers Comp Doctor Never lie about prior injuries, pre-existing conditions, or medical history. Never lie about the extent of your workplace injury or how it happened. Do not exaggerate your symptoms, including pain or functionality.
Form DWC-1 Employers First Report of Injury or Occupational Disease. The employer is required to submit this form with EMPLOYERS and the injured employee or the injured employees attorney within eight days after the employees absence from work or notice of the Injury or Occupational Disease.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

Because workers compensation is not taxable, you will not receive a 1099 or W-2 form for any workers comp payouts. However, if youre receiving wages from any light-duty work, disability insurance payments, or Social Security benefits, you will receive the appropriate tax forms.
DWC-7 Notice to Employees-Injuries Caused by Work (English and Spanish). This form provides your employees with information regarding workers compensation benefits and the Medical Provider Network (MPN) in California.

Related links

Fla. Admin. Code Ann. R. 69L-7.720 - Forms Incorporated by

(a) A copy of the Form DFS-F5-DWC-9 can be obtained from the AMA website at . Completion instructions for the DFS-F5-DWC-9Read more

Learn more
Florida Workers Compensation Uniform Medical Treatment

Florida Workers Compensation Uniform Medical Treatment/Status Reporting Form - PAGE 1. BEFORE COMPLETING THIS FORM, PLEASE CAREFULLY REVIEW THERead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here