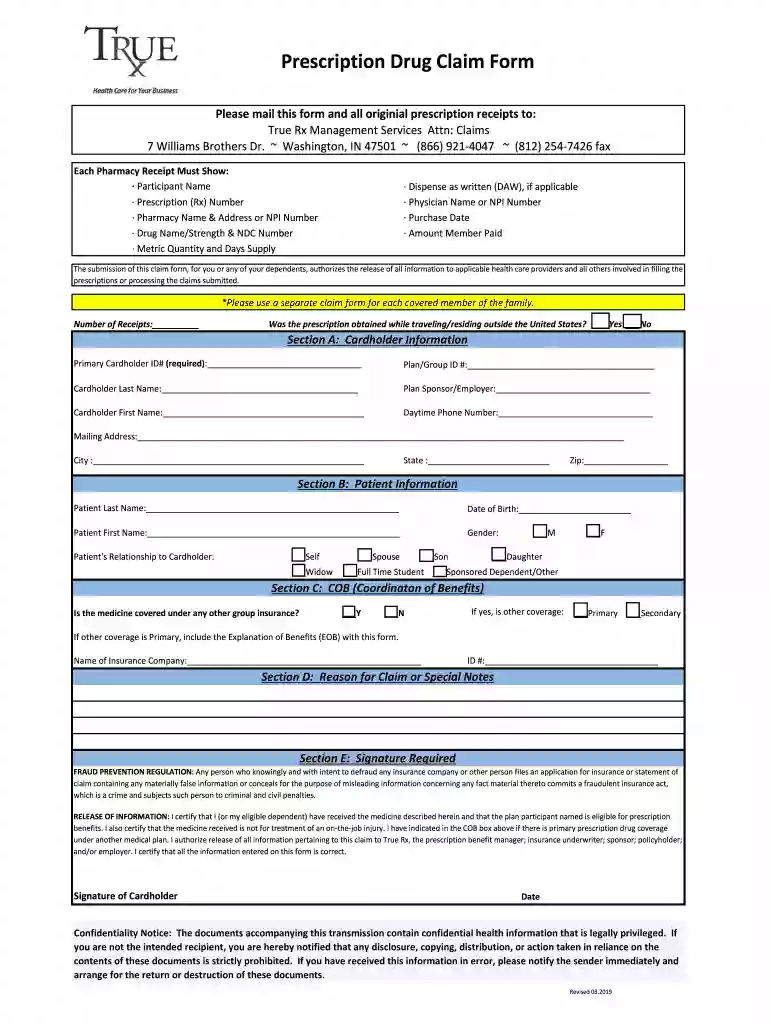
trucard rx prior authorization form Preview on Page 1

True rx form 2026

Here's how it works

  • 01. Edit your trucard rx prior authorization form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out true rx form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the true rx form in the editor.
  2. Begin with Section A: Cardholder Information. Fill in your Primary Cardholder ID#, Plan/Group ID#, last and first name, daytime phone number, and mailing address. Ensure all details are accurate.
  3. Proceed to Section B: Patient Information. Enter the patient's last and first name, date of birth, gender, and their relationship to the cardholder. Select the appropriate option from the provided choices.
  4. In Section C: Coordination of Benefits (COB), indicate if the medicine is covered under any other group insurance by selecting 'Yes' or 'No'. If applicable, provide details about the other coverage.
  5. Use Section D for any special notes or reasons for your claim. This is your opportunity to provide additional context if necessary.
  6. Finally, complete Section E by signing and dating the form to certify that all information is correct and that you authorize release of information pertaining to this claim.

Start filling out your true rx form today on our platform for free!

See more trucard rx prior authorization form versions

We've got more versions of the trucard rx prior authorization form form. Select the right trucard rx prior authorization form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20194.8 Satisfied (112 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

(1) The doc has filled your prescription - meaning the doc wrote a prescription for me, but I still need to go to a pharmacy to get my medicine. For now, I have not been charged for the medicine. (2) The pharmacist has filled your prescription - meaning the pharmacist provided the medicine to me.
Were your pharmacy insurance provider. You will continue to receive medications at your local pharmacy while we work in the background to make sure youre getting prescriptions with ease and accuracy.
Prior authorization requires your doctor or provider to obtain approval from your health plan before providing health care services or prescribing prescription drugs. Without prior authorization, your health plan may not pay for your treatment or medication. (Emergency care doesnt need prior authorization.)
Prescription Drugs (Rx)
This is short for the word prescription. Doctors use prescriptions to tell pharmacists (the people who prepare medicines in drugstores and hospitals) what medicine to give you.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

The Rx symbol was used as an abbreviation for recipe and was commonly placed at the beginning of a prescription to instruct the pharmacist or patient to take certain ingredients or medicines. Over time, the Rx symbol evolved from the Latin recipe abbreviation.

Related links

Prescription Reimbursement Claim Form Important!

Allow up to 30 calendar days for processing to receive a response to your claim. Keep a copy of all documents submitted for your records.Read more

Learn more
Part 80: Rules and Regulations on Controlled Substances in

(1) pharmacy prescription number;. (2) pharmacys national identification number;. (3) patient name;. (4) patient address, including street, city, state, ZIPRead more

Learn more
PRIOR AUTHORIZATION REQUEST FORM

PRIOR AUTHORIZATION REQUEST FORM. Fax to (812) 254-7426. Please note Have any other prescription medications been tried in the past for this diagnosis?Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here