




Here's how it works
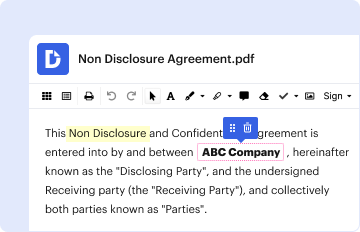
01. Edit your odm 06723 online
Type text, add images, blackout confidential details, add comments, highlights and more.
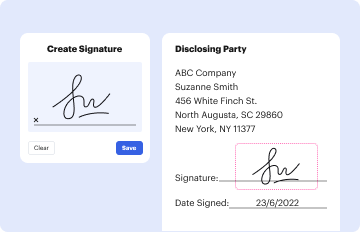
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send ohio medicaid authorized representative form via email, link, or fax. You can also download it, export it or print it out.
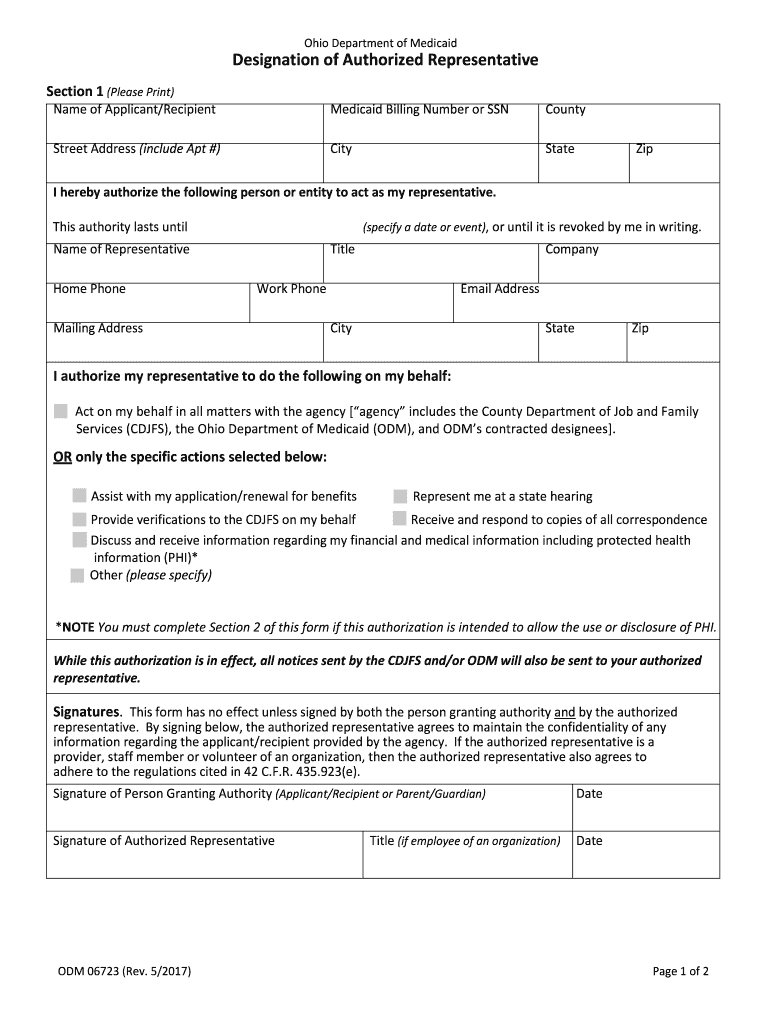
How to use or fill out odm 06723 with our platform

- Click ‘Get Form’ to open the odm 06723 in the editor.
- Begin by filling out Section 1 with your personal information, including your name, Medicaid Billing Number or SSN, and address details. Ensure all fields are completed accurately.
- Designate your authorized representative by entering their name, contact information, and title. Specify the duration of this authorization clearly.
- Select the actions you authorize your representative to perform on your behalf. You can choose from options like assisting with applications or representing you at hearings.
- In Section 2, provide details for the authorization of protected health information (PHI). Fill in necessary identifiers such as case number and date of birth.
- Review all entries for accuracy before signing. Both you and your authorized representative must sign and date the form for it to be valid.
Start using our platform today to easily complete and manage your odm 06723 form online for free!
Fill out odm 06723 online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


