




Here's how it works
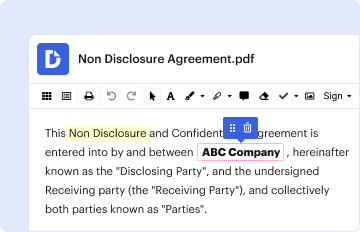
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
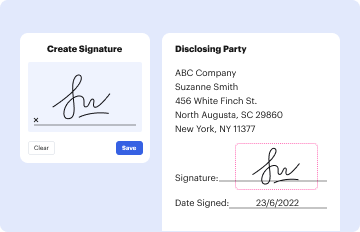
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
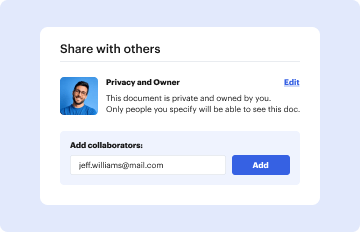
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out medical authorization form with our platform

- Click ‘Get Form’ to open the medical authorization form in the editor.
- Begin by entering the name of the health care provider in the designated field. This identifies who will be releasing the information.
- Fill in the client’s name, date of birth, and social security number. These details are crucial for accurately identifying the patient.
- Specify the name of the attorney or representative who will receive the information. Ensure this is correct to avoid any delays.
- In the exceptions section, clearly outline any specific information that should not be released. This protects sensitive data.
- Sign and date the form at the bottom to authorize release. Remember, your signature confirms consent for sharing your medical records.
- If applicable, have the requesting party sign and date their section to validate their request for information.
Start using our platform today to easily complete your medical authorization form online for free!
Fill out medical authorization form online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


