





Here's how it works
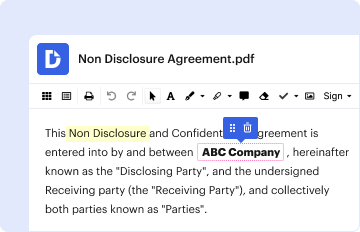
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
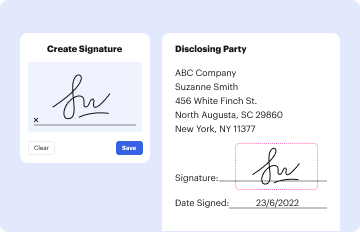
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
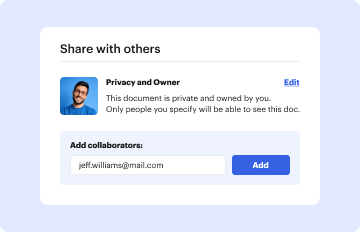
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out dd mo ef 5 13 with our platform

- Click ‘Get Form’ to open the dd mo ef 5 13 in the editor.
- Begin with Section 1, where you will input your Employee Information. Fill in details such as Group Name, Group Number, and your personal information including First Name, Last Name, Social Security Number, and Date of Birth.
- Proceed to Section 2 for Spouse and Dependent Information. Here, list any dependents you wish to enroll or cancel. Ensure you check the appropriate boxes for enrollment status.
- In Section 3, answer questions regarding Coordination of Benefits. This section helps determine if you have other dental coverage through a spouse or other means.
- Move on to Section 4 for any Change of Coverage requests. Indicate if you're adding or cancelling coverage and provide necessary details about the changes.
- Finally, complete Section 5 by signing and dating the form to authorize your application. Make sure all information is accurate before submission.
Start using our platform today for free to streamline your form completion process!
Fill out dd mo ef 5 13 online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


