




Here's how it works
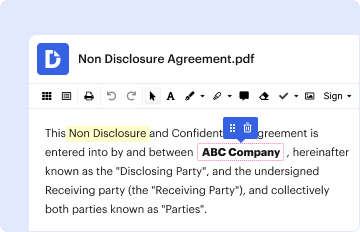
01. Edit your mount sinai hipaa release form online
Type text, add images, blackout confidential details, add comments, highlights and more.
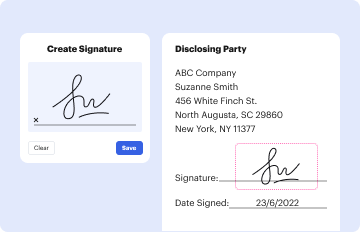
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
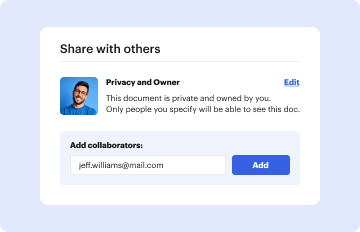
03. Share your form with others
Send site dochub com people media via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Authorization to Disclose to Third Party - Mount Sinai Hospital - mountsinai

- Click ‘Get Form’ to open it in the editor.
- Begin by entering the patient's name, date of birth, and contact information in the designated fields. Ensure accuracy for proper identification.
- Select the specific medical information you wish to disclose by checking the appropriate boxes. This includes options for emergency room visits, outpatient clinic visits, hospitalizations, and more.
- Indicate whether the records include sensitive information such as HIV-related data or psychiatric records by checking 'do include' or 'do not include'.
- Specify the recipient of the disclosed information by selecting from options like healthcare provider, insurance company, or other entities. Fill in their name and address.
- Provide a reason for disclosure by checking 'Patient Request' or specifying another reason in the provided field.
- Sign and date the authorization at the bottom of the form. If applicable, have a personal representative sign as well.
Start using our platform today to easily complete your Authorization to Disclose form online for free!
Fill out Authorization to Disclose to Third Party - Mount Sinai Hospital - mountsinai online
It's free
It's free
See more Authorization to Disclose to Third Party - Mount Sinai Hospital - mountsinai versions
We've got more versions of the Authorization to Disclose to Third Party - Mount Sinai Hospital - mountsinai form. Select the right Authorization to Disclose to Third Party - Mount Sinai Hospital - mountsinai version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


