po box 1870 Preview on Page 1

Treatment report form 2026

Here's how it works

  • 01. Edit your po box 1870 online

    Type text, add images, blackout confidential details, add comments, highlights and more.

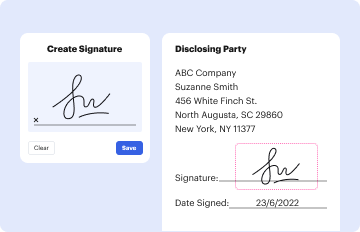
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send po box 1870 hicksville ny 11802 via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out treatment report form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the treatment report form in the editor.
  2. Begin by filling out the Identifying Data section. Enter the patient's name, Medicaid ID, date of birth, and address details accurately to avoid delays.
  3. Next, move to the Provider Information section. Input your name, Tax ID, phone number, and details of any other behavioral health providers involved in the patient's care.
  4. In the DSM-IV TR Diagnosis section, select appropriate diagnoses from AXIS I through V based on the patient’s condition. Be thorough in documenting any relevant symptoms.
  5. Complete the Current Clinical Information section by assessing current risk factors such as suicide or homicide ideation and any history of abuse.
  6. Document the Patient’s Treatment History including all levels of care and specify treatment goals along with objective outcome criteria for measuring success.
  7. Finally, review all entries for accuracy before signing and dating at the bottom of the form. Ensure that all required fields are completed to facilitate processing.

Start using our platform today to streamline your treatment report form completion for free!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

beacon po box 1870 hicksville ny

Individual Animal Health Treatment Form

INDIVIDUAL ANIMAL HEALTH TREATMENT REPORTING FORM. Date: ID. Name. Location Describe treatment administered and any other information. Initials.Read more

Learn more
for Form FDA 3500A MedWatch (for Mandatory reporting)

List and provide product names and therapy dates for any other medical products (drugs, biologics, including human cells, tissues, and cellular and tissue-basedRead more

Learn more
Monthly Treatment Report

This form must be completed and submitted with. MONTHLY TREATMENT REPORT each monthly billing. Additional sheets may be used. 1. PROGRAM NAME: 1a. PROVIDERRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here