wcb case number lookup Preview on Page 1

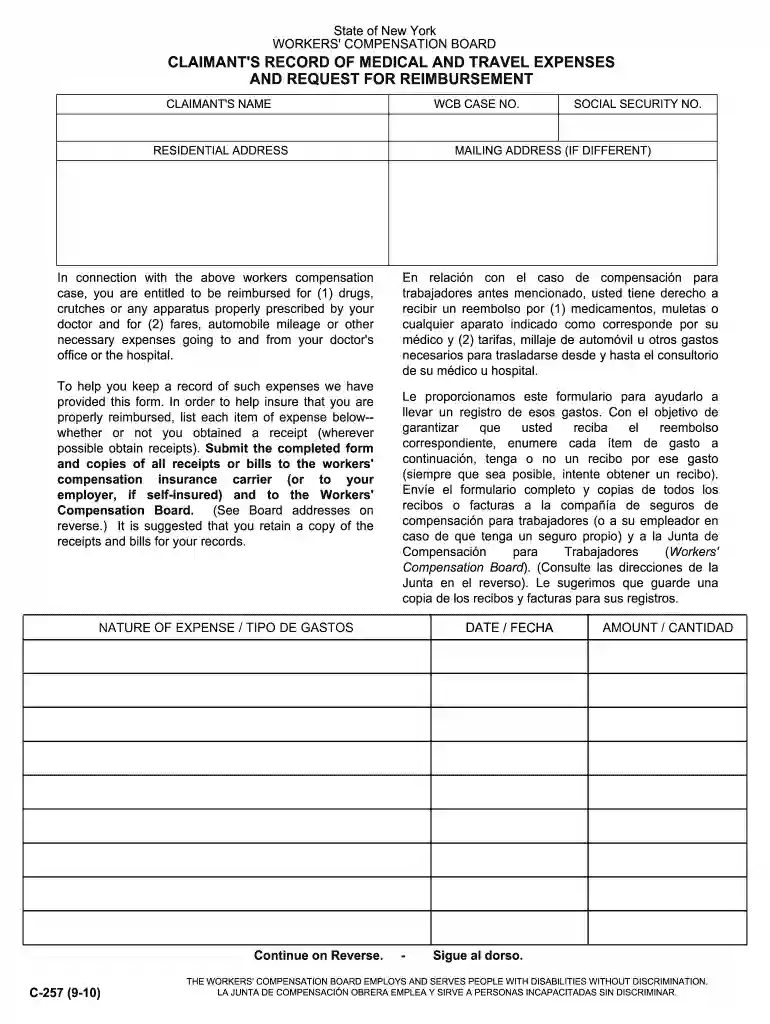
State of New York WORKERS ' COMPENSATION BOARD CLAIMANT 'S RECORD OF MEDICAL AND TRAVEL EXPENSES AND REQUEST FOR REIMBURSEMENT CLAIMANT 'S NAME WCB CASE NO - clarkson 2026

Here's how it works

  • 01. Edit your wcb case number lookup online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send nys workers comp mileage reimbursement 2022 via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out State of New York WORKERS' COMPENSATION BOARD CLAIMANT'S RECORD OF MEDICAL AND TRAVEL EXPENSES AND REQUEST FOR REIMBURSEMENT CLAIMANT'S NAME WCB CASE NO - clarkson

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by entering your name and WCB case number at the top of the form. Ensure that all information is accurate to avoid delays in processing.
  3. Fill in your residential address and, if applicable, a different mailing address. This ensures that any correspondence regarding your reimbursement reaches you promptly.
  4. In the 'Nature of Expense' section, list each medical or travel expense incurred. Be specific about the type of expense, such as medications or transportation costs.
  5. For each expense, provide the date it was incurred and the amount spent. If you have receipts, make sure to keep copies for your records.
  6. Once completed, submit the form along with any receipts to your workers' compensation insurance carrier or employer. Retain a copy for your own records.

Start using our platform today to streamline your reimbursement process for free!

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

Electronic signatures are an excellent alternative to traditional signing, as they save time, effort, and costs people spend on printing, scanning, and paper delivery. You can eSign your State of New York WORKERS ' COMPENSATION BOARD CLAIMANT 'S RECORD OF MEDICAL AND TRAVEL EXPENSES AND REQUEST FOR REIMBURSEMENT CLAIMANT 'S NAME WCB CASE NO - clarkson using a trustworthy and powerful online document processing services like DocHub. It complies with major eSignature regulations (ESIGN and UETA), so all documents approved there are legally binding and have the same validity as manually signed ones.

When you go for analog ways of completing your State of New York WORKERS ' COMPENSATION BOARD CLAIMANT 'S RECORD OF MEDICAL AND TRAVEL EXPENSES AND REQUEST FOR REIMBURSEMENT CLAIMANT 'S NAME WCB CASE NO - clarkson, you can easily download your file for printing. Search DocHub’s Forms & Templates catalog to get the exact file template you need and open it for editing or download it on your device in the format of your liking. It is easy to complete your form electronically and place your handwritten signature on it right after printing or eSign your file with DocHub.

1. Within five days but no more than 14 days from receipt of a medical treatment request by a treating physician, a utilization review determination should be made as to whether the request is authorized, delayed or rejected. If the determination is delayed, it's because additional information has been requested.
EMPLOYEE'S CLAIM FOR COMPENSATION/REPORT OF INITIAL TREATMENT. FORM C-4.
Compensation Rates An injured employee is entitled to a compensation rate equal to two-thirds of the average weekly wage (AWW) in New York State for the 52-week period immediately prior to the date of accident. The rate is subject to prescribed maximums and degree of disability.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

The formula used by the New York State Workers' Compensation Board to calculate weekly settlement payments is as follows: Weekly Rate: 2/3 x average weekly wage x % of disability (for example, partial disability or temporary disability)
(t) "Request for authorization" 1 defines Request for Authorization as a written request for a specific course of proposed medical treatment. An RFA must meet both of the following criteria: Only for medical treatment and. Must be written.
Accordingly, an employer's annual payroll, in $100 units, is multiplied by a price or \u201crate\u201d (which reflects the nature of the work) to determine the annual premium. This premium is modified, where appropriate, to reflect the individual employer's safety record.
Report of Termination of Disabilty. and/or Payment. U.S. Department of Labor. Form CA-3.
The New York State Workers' Compensation Law Judge sets the amount of the fee, which generally is between 10 and 15 percent of the award.

Related links

New York State Department of State - NY.gov

Jan 6, 2016 State agencies must specify in each notice which proposes a rule the last date on which they will accept public comment.Read more

Learn more
Q14-43 Medicaid Eligibility Assistance

Jan 29, 2014 Contractor shall indemnify, defend and hold harmless the. State University of New York, the State of New York and SUNY-DMC (the Indemnified).Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here