


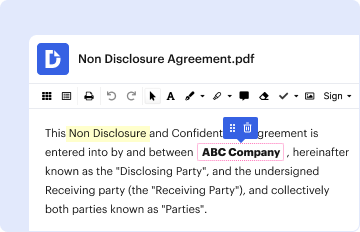
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.


Type text, add images, blackout confidential details, add comments, highlights and more.
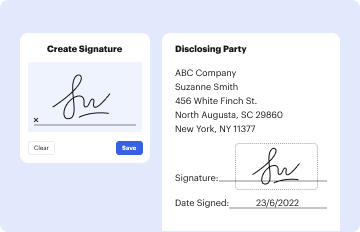
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
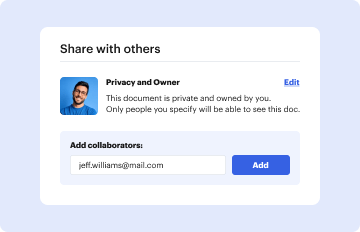
Send it via email, link, or fax. You can also download it, export it or print it out.
The Medi-Cal Choice Form is designed for Californians enrolling or changing their health plans under the Department of Health Care Services. This crucial document helps individuals select, modify, or confirm their participation in a Medi-Cal health plan. It emphasizes the importance of capturing personal data, such as contact information and health plan preferences, all while ensuring confidentiality and compliance with state-specific health regulations. This form serves as a vital tool in maintaining streamlined healthcare transitions and enrollment accuracy.
To obtain the free fillable Medi-Cal Choice Form, users can visit online platforms like DocHub, which host secure, fillable versions of the form. These can be accessed and downloaded directly using a compatible device. Alternatively, paper versions may be requested from local health offices or state websites related to the California Department of Health Care Services. Utilizing digital platforms ensures quicker access and facilitates easier completion and submission of the document, particularly for those with tight schedules or limited mobility.
Completing the Medi-Cal Choice Form involves several key steps, ensuring that all necessary information is accurately provided:
The Medi-Cal Choice Form comprises several critical components, each designed to capture specific information:
The legal use of the Medi-Cal Choice Form mandates that all information be used solely for health plan enrollment and modifications under California's Health Care guidelines. The form underscores strict confidentiality measures to protect personal data during processing. Users are assured that their information is handled following legal standards, providing peace of mind regarding privacy and data security when engaging in state healthcare actions.
The Medi-Cal Choice Form is most commonly used by California residents eligible for Medi-Cal who need to enroll or change health plans. This includes individuals undergoing significant life changes—such as moving locations or experiencing shifts in employment or family size—that necessitate a reevaluation of their healthcare needs. It's a critical document for ensuring that healthcare coverage remains consistent and tailored to the individual’s current circumstances.

California-specific regulations govern the application and submission of the Medi-Cal Choice Form:
Scenario 1: A family recently moved within California and needs to change their healthcare provider to one within their new locality. They use the Medi-Cal Choice Form to update their plan, ensuring uninterrupted care.
Scenario 2: A single parent on Medi-Cal realizes their current plan does not sufficiently cover their children's pediatric needs. They explore options through the Medi-Cal Choice Form to switch to a plan with better pediatric provisions.
Scenario 3: An individual nearing retirement is currently on a Medicaid plan through their employer. As they transition, using the Medi-Cal Choice Form helps them maintain constant coverage without service interruptions.
We've got more versions of the Free fillable Medi-Cal Choice Form Mail form back to form. Select the right Free fillable Medi-Cal Choice Form Mail form back to version from the list and start editing it straight away!
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.








Complete and sign the form, then submit it by one of these methods: Mail: 6655 Alvarado Road, San Diego CA 92120 Fax: 619-543-7128 Drop off on-site (no same-
Download forms FAQs Home. Download Forms. Choose a county from the drop down list to see materials for that county. Choose your county: County Options.Read more


