




Here's how it works
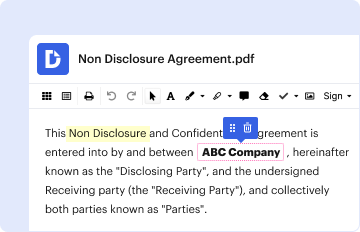
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
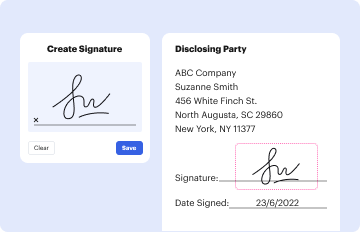
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
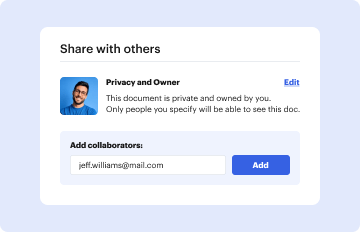
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out PHYSICIAN S STATEMENT FOR DEATH CLAIMS - cisp coop with our platform

- Click ‘Get Form’ to open it in the editor.
- Begin by entering the NAME OF DECEASED, RESIDENCE AT DEATH, APPARENT AGE AT DEATH, DATE OF DEATH, and PLACE OF DEATH in the designated fields.
- For question 1, provide a detailed response regarding the immediate cause of death. Ensure clarity for accurate processing.
- In question 2, list any contributing factors or diseases that led to the death. Specify the duration of these contributory causes.
- Question 3 requires you to describe the first indication of failing health and when these signs were first noticed.
- For question 4, indicate if there were other diseases suffered by the deceased. Mark applicable options and provide diagnosis dates.
- Proceed to questions 5 through 9, answering each carefully based on your knowledge and observations as the attending physician.
- Finally, certify your statements by signing and providing your full name, license number, clinic address, and contact information.
Start using our platform today for free to complete your PHYSICIAN S STATEMENT FOR DEATH CLAIMS efficiently!
Fill out PHYSICIAN S STATEMENT FOR DEATH CLAIMS - cisp coop online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


