




Here's how it works
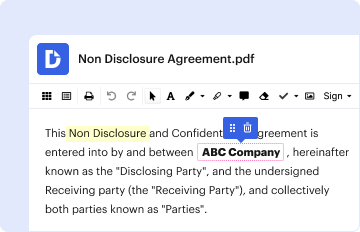
01. Edit your seaview ipa authorization form online
Type text, add images, blackout confidential details, add comments, highlights and more.
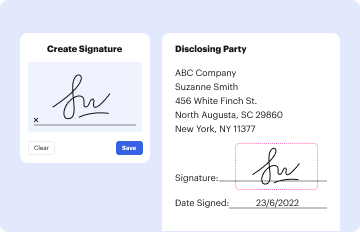
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
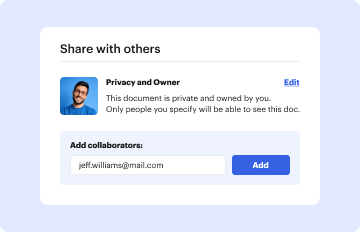
03. Share your form with others
Send ipa referral authorization form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out seaview ipa authorization form with our platform

- Click ‘Get Form’ to open the seaview ipa authorization form in the editor.
- Begin by entering the patient information. Fill in the patient's name, sex, address, date of birth, co-pay amount, city/state, member ID number, phone number, health plan name, plan code, and zip code.
- Next, specify the primary care physician (PCP) and indicate if there is other insurance coverage. If yes, provide the name and fax number of the other insurance provider.
- In the 'Prior Authorization Request' section, enter the ICD-9 and CPT codes relevant to the services requested. Provide a detailed description of the procedure or service along with frequency/duration requested.
- Complete the treatment plan and specify the hospital or facility where services will be provided. Include expected date of admission and details about any assistant surgeon if applicable.
- Finally, have the physician print their name, sign, and date at the bottom of the form. Ensure all sections are filled accurately before submission.
Start using our platform today to easily fill out your seaview ipa authorization form for free!
Fill out seaview ipa authorization form online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Consent to Easement
The document is a 'Consent to Easement' agreement where a property owner grants an easement and right of way to a consen ...

Name Change Request for Adults
The document is an application form for adults requesting a name change in Prato, Italy. It requires personal informatio ...
California Elder Abuse Report Form
The document is a confidential report form used by the California Department of Social Services to report suspected abus ...

Life Insurance Data Capture Form
The document is a Data Capture Form for a proposed Life Insurance policy, detailing sections for adviser and client info ...

USCIS AR-11 Alien's Change of Address Card
The document is the AR-11, Alien's Change of Address Card, required by U.S. Citizenship and Immigration Services for ali ...

Italian Residential Lease Agreement
The document is a real estate lease proposal outlining the terms and conditions for renting a property. It includes deta ...

ADHD Medication Prior Authorization Form
The document outlines the prior authorization process for ADHD medications for children under 6 years old through Mercy ...

First Home Visit Questionnaire
The document is a First Home Visit Questionnaire designed to gather essential information about a child's family backgro ...