




Here's how it works
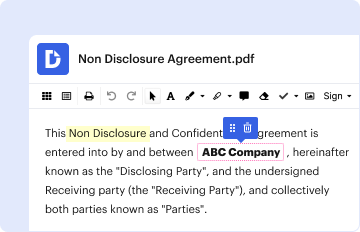
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
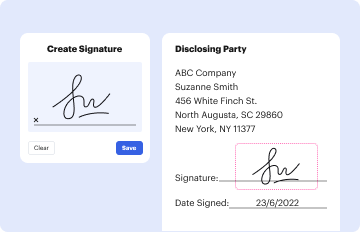
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
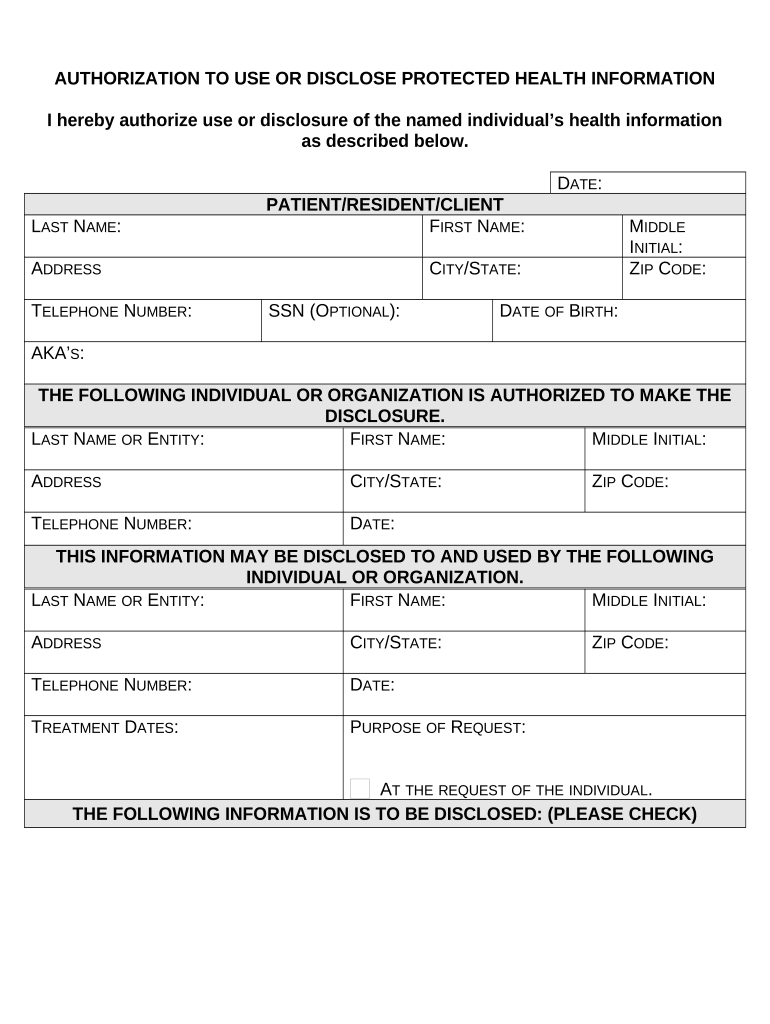
How to use or fill out authorization use health information form with our platform

- Click ‘Get Form’ to open the authorization use health information form in the editor.
- Begin by entering the date at the top of the form, followed by the patient's last name, first name, and middle initial. Fill in their address, telephone number, city/state, zip code, and optional SSN.
- Identify the individual or organization authorized to make the disclosure by filling in their last name or entity, first name, middle initial, address, city/state, telephone number, and zip code.
- Next, specify who may receive this information by completing the same fields for the recipient as you did for the disclosing party.
- Indicate treatment dates and purpose of request clearly. Then check all applicable boxes regarding what specific health information is to be disclosed.
- Review sections on sensitive information and rights. Specify an expiration date if desired; otherwise, it will default to one year from signing.
- Finally, sign and date at the bottom of the form. If signed by a legal representative, include their relationship to the individual.
Start using our platform today for free to easily complete your authorization use health information form!
Fill out authorization use health information form online
It's free
It's free
Got questions?
We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.
Contact us
How to fill out authorization for use and disclosure of protected health information?
Begin by specifying your name, the entity authorized to disclose information, and the individuals or entities you authorize to receive it. Indicate the specific information and purpose for which it will be disclosed, add an expiration date or event, and sign and date the form to confirm your consent.
What is an example of a HIPAA authorization?
I hereby authorize use or disclosure of protected health information about me as described below. 4. I understand that the information used or disclosed may be subject to re-disclosure by the person or class of persons or facility receiving it, and would then no longer be protected by federal privacy regulations.
What are two required elements of an authorization needed to disclose PHI?
45 CFR 164.508: (i) A description of the information to be used or disclosed that identifies the information in a specific and meaningful fashion. (ii) The name or other specific identification of the person(s), or class of persons, authorized to make the requested use or disclosure.
What is an authorization for use and disclosure of health information?
A Privacy Rule Authorization is an individuals signed permission to allow a covered entity to use or disclose the individuals protected health information (PHI) that is described in the Authorization for the purpose(s) and to the recipient(s) stated in the Authorization.
What is an authorization form?
What is an Authorization Form? An authorization form is a document that is duly endorsed by an individual or organisation which grants permission to another individual or organisation to proceed with certain actions. It is often used to grant permission to carry out a specific action for a fixed period of time.
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Animalhealthservicestcigmailcom form
The document outlines the application process for importing animal products and pets into the Turks and Caicos Islands, ...
573 522 4989
The document is a Business Activity Questionnaire (Form 4458) from the Missouri Department of Revenue, designed to colle ...

Fee Waiver Application - Maricopa County - maricopa
The document outlines the application process for a fee waiver for permit fees related to charitable nonprofit establish ...

Download the Notice of Claim Form - Utah Transit Authority
The document outlines the procedure for filing a claim against the Utah Transit Authority, detailing required forms and ...

Worksheet of a e i form
The document is a worksheet for calculating child support obligations in Arizona, detailing the financial information re ...

School Year 2012-2013 Student Enrollment Informa on - eliothinemiddleschool
The document provides enrollment information for families wishing to enroll their children in the District of Columbia P ...
People also ask
What does authorization to disclose health information mean?
HIPAA authorization is consent obtained from a patient or health plan member that permits a covered entity or business associate to use or disclose PHI to an individual/entity for a purpose that would otherwise not be permitted by the HIPAA Privacy Rule.
Should I agree or decline HIPAA authorization?
If you do not have sufficient information to make an informed decision, you should always decline a HIPAA authorization request. The HIPAA Privacy Rule stipulates that Protected Health Information (PHI) can only be used or disclosed by covered entities and business associates for required or permitted purposes.