form 16 1 Preview on Page 1

FORM 16-1 AUTHORIZATION FOR USE OR DISCLOSURE OF HEALTH ... 2026

Here's how it works

  • 01. Edit your form 16 1 online

    Type text, add images, blackout confidential details, add comments, highlights and more.

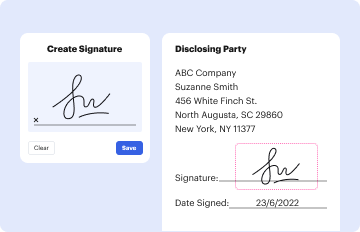
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
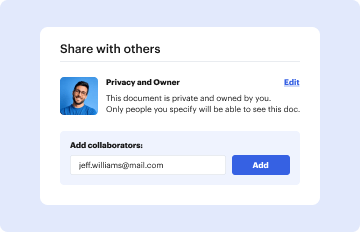
  • 03. Share your form with others

    Send 16 1 form via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out FORM 16-1 AUTHORIZATION FOR USE OR DISCLOSURE OF HEALTH INFORMATION

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. In the first section, enter the name of the person or organization you are authorizing to release your health information.
  3. Next, specify the recipients of this information by filling in their names and addresses accurately.
  4. Indicate whether you authorize all health information or only specific records by checking the appropriate box and providing details if necessary.
  5. Select any specific types of sensitive information you wish to disclose, such as mental health treatment or HIV test results.
  6. State the purpose for which this information is being disclosed, choosing from options like 'patient request' or specifying another reason.
  7. Fill in the expiration date for this authorization to ensure clarity on its validity period.
  8. Sign and date the form at the bottom, ensuring that if someone else signs on your behalf, they indicate their legal relationship to you.

Start using our platform today to easily complete your FORM 16-1 for free!

See more form 16 1 versions

We've got more versions of the form 16 1 form. Select the right form 16 1 version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20094.1 Satisfied (55 Votes)
20034 Satisfied (59 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

Authorization. A covered entity must obtain the individuals written authorization for any use or disclosure of protected health information that is not for treatment, payment or health care operations or otherwise permitted or required by the Privacy Rule.
I hereby authorize use or disclosure of protected health information about me as described below. 4. ​ I understand that the information used or disclosed may be subject to re-disclosure by the person or class of persons or facility receiving it, and would then no longer be protected by federal privacy regulations.
Begin by specifying your name, the entity authorized to disclose information, and the individuals or entities you authorize to receive it. Indicate the specific information and purpose for which it will be disclosed, add an expiration date or event, and sign and date the form to confirm your consent.
Signing a HIPAA authorization form allows a healthcare agent to question a doctor about charges on a bill, provide PHI to an attorney for an accident claim, and allow someone helping with medical bill payment to check their payment. You remain safe even if someone gains access to your information.
Clearly state your name and that youre writing to grant authorization to another individual or organization. In the body of your letter, identify the parties involved, specify the authority youre granting, define the duration, and include any other necessary information.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

Should you sign a HIPAA authorization form? In most cases, the answer is yes. HIPAA is designed to protect patients sensitive health information. Following all HIPAA rules can help to protect healthcare professionals from legal trouble and allow them to better serve their patients.
A Privacy Rule Authorization is an individuals signed permission to allow a covered entity to use or disclose the individuals protected health information (PHI) that is described in the Authorization for the purpose(s) and to the recipient(s) stated in the Authorization.

Related links

Use And Disclosure Of Phi Substance Abuse

rization for Use or Disclosure of Health Information form. (CHA Form 16-1), found in chapter 7, complies with these regulatory requirements and with otherRead more

Learn more
Army Reguation 40-66: Medical Record Administration and

A completed Authorization for Release of Medical Information included in Standard Form (SF) 86 (Questionnaire for National Security Positions) is required forRead more

Learn more
EPA

This report describes the accumulation of chemical contaminants in river, lake, ocean, and estuary bottoms and includes a screening assessment of the potentialRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here