


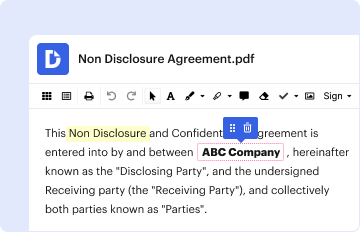
01. Edit your blue dental claim form online
Type text, add images, blackout confidential details, add comments, highlights and more.

Type text, add images, blackout confidential details, add comments, highlights and more.
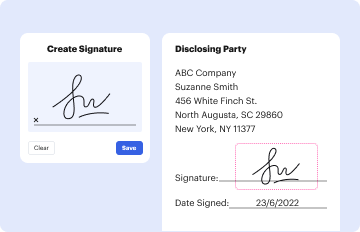
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
Send blue dental claim via email, link, or fax. You can also download it, export it or print it out.

Start using our platform today for free to streamline your dental claims process!
We've got more versions of the blue dental claim form form. Select the right blue dental claim form version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2023 | 4.4 Satisfied (32 Votes) | |
| 2023 | 4.2 Satisfied (49 Votes) | |
| 2022 | 4.8 Satisfied (55 Votes) | |
| 2020 | 4.8 Satisfied (247 Votes) | |
| 2020 | 4.8 Satisfied (101 Votes) | |
| 2020 | 4.4 Satisfied (134 Votes) | |
| 2020 | 4.8 Satisfied (261 Votes) | |
| 2020 | 4.8 Satisfied (117 Votes) | |
| 2020 | 4.3 Satisfied (26 Votes) | |
| 2020 | 4.7 Satisfied (51 Votes) | |
| 2020 | 4.2 Satisfied (36 Votes) | |
| 2020 | 4.1 Satisfied (59 Votes) | |
| 2020 | 4.5 Satisfied (39 Votes) | |
| 2019 | 4.8 Satisfied (130 Votes) | |
| 2019 | 4.8 Satisfied (79 Votes) |
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
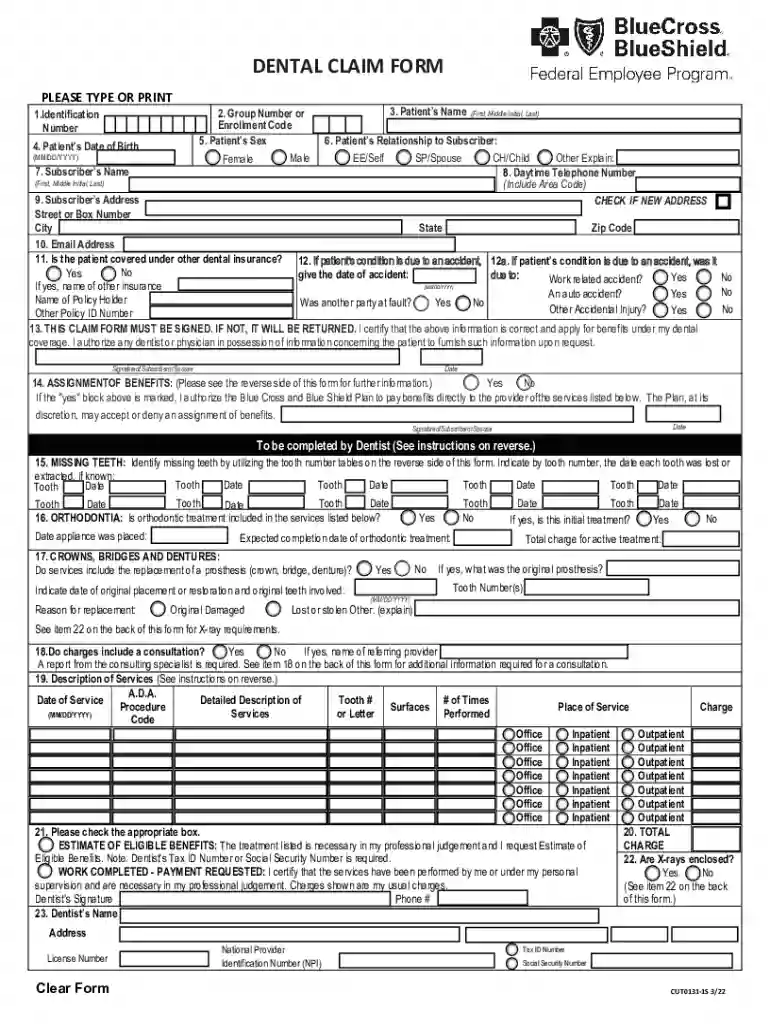
Send completed claim form to: Blue Cross and Blue Shield of Massachusetts P.O. Box 986030 Boston MA 02298 r submit claims must be submitted within two years of
MAIL FEP DENTAL CLAIM FORMS TO: BlueCross BlueShield of South Carolina , South Carolina 29407-3383 Phone Number: 1-800-444-4325
If damage or loss is discovered, file a claim with the carrier immediately. Blue label cartridges are available levels in case of momentary acci- dental


