




Here's how it works
01. Edit your emory medical records online
Type text, add images, blackout confidential details, add comments, highlights and more.
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send emory medical records request via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Authorization to Release Medical Information - Emory Healthcare with our platform

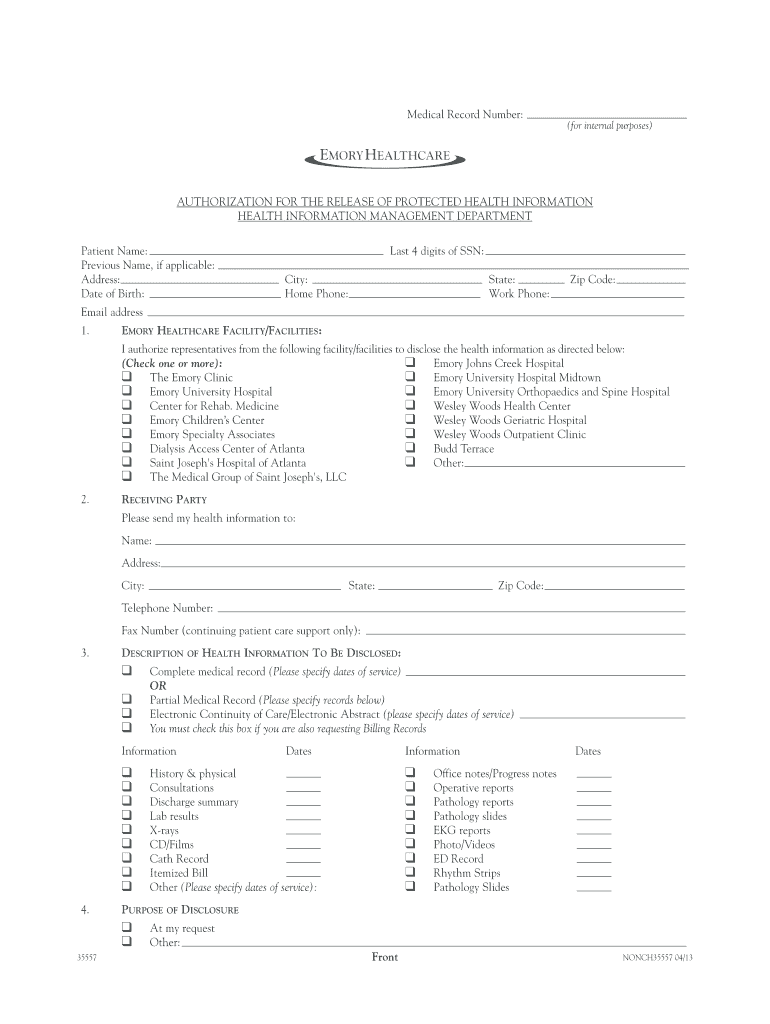
- Click ‘Get Form’ to open the Authorization to Release Medical Information in the editor.
- Begin by entering your Medical Record Number at the top of the form for internal tracking.
- Fill in your personal details, including your name, last four digits of your SSN, previous name (if applicable), address, date of birth, and contact numbers.
- Select the Emory Healthcare facility or facilities from which you authorize the release of your health information by checking the appropriate boxes.
- Provide details about the receiving party by filling in their name, address, and contact information.
- Specify what health information you wish to disclose by selecting either 'Complete medical record' or 'Partial Medical Record' and detailing any specific records needed.
- Indicate the purpose for this authorization by checking 'At my request' or specifying another reason.
- Set an expiration date for this authorization; if left blank, it will automatically expire after 90 days.
- Review all sections carefully before signing and dating the form at the bottom. Ensure that a copy is provided to you for your records.
Start using our platform today to easily complete and manage your medical release forms online for free!
Fill out Authorization to Release Medical Information - Emory Healthcare - emoryhealthcare online
It's free
It's free
See more Authorization to Release Medical Information - Emory Healthcare - emoryhealthcare versions
We've got more versions of the Authorization to Release Medical Information - Emory Healthcare - emoryhealthcare form. Select the right Authorization to Release Medical Information - Emory Healthcare - emoryhealthcare version from the list and start editing it straight away!
Got questions?
We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.
Contact us
What are the 8 requirements of a valid authorization to release information?
8 Key Elements of a Compliant Medical Records Release Form Patient Information. Purpose of Request. Dates of Service. Recipient Information. Valid Authorization Signature. Date of Signature. Restrictions or Limitations. Revocation Clause.
How to fill out authorization for release and use of medical information?
0:43 1:58 A description of the protected. Health information to be used and disclosed. The person authorizedMoreA description of the protected. Health information to be used and disclosed. The person authorized to make the use or disclosure. The person to whom the covered entity may make the disclosure.
What is an authorization letter for medical purposes on my behalf?
How to Write a Medical Authorization Letter. Begin with your full name, address, and contact information, followed by the current date. These details identify the author of the letter. Clearly mention the name and relationship of the person or organization being authorized to act on your behalf.
What is an example of a HIPAA authorization?
I hereby authorize use or disclosure of protected health information about me as described below. 4. I understand that the information used or disclosed may be subject to re-disclosure by the person or class of persons or facility receiving it, and would then no longer be protected by federal privacy regulations.
Do you authorize the release of medical information?
Your health information cannot be used or shared without your written permission unless this law allows it. For example, without your authorization, your provider generally cannot: Give your information to your employer. Use or share your information for marketing or advertising purposes or sell your information.
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


People also ask
How to fill out authorization to release information?
Begin by specifying your name, the entity authorized to disclose information, and the individuals or entities you authorize to receive it. Indicate the specific information and purpose for which it will be disclosed, add an expiration date or event, and sign and date the form to confirm your consent.
How do you write an authorization letter for medical records release?
I, the undersigned, authorize the release of, or request access to the information specified below from the medical record(s) of the above name patient. I understand that my records are confidential and cannot be disclosed without my written authorization, except when otherwise permitted by law.
Which scenario requires an authorization to release medical records?
Common scenarios where a signed release form is required include: Sharing medical records with a family member. A healthcare professional cant send test results to a spouse or parent unless the patient has given written permission. Sending records to an insurance company or attorney.


