01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.

Type text, add images, blackout confidential details, add comments, highlights and more.
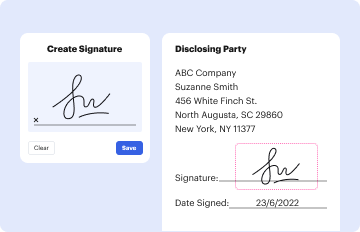
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
Send it via email, link, or fax. You can also download it, export it or print it out.
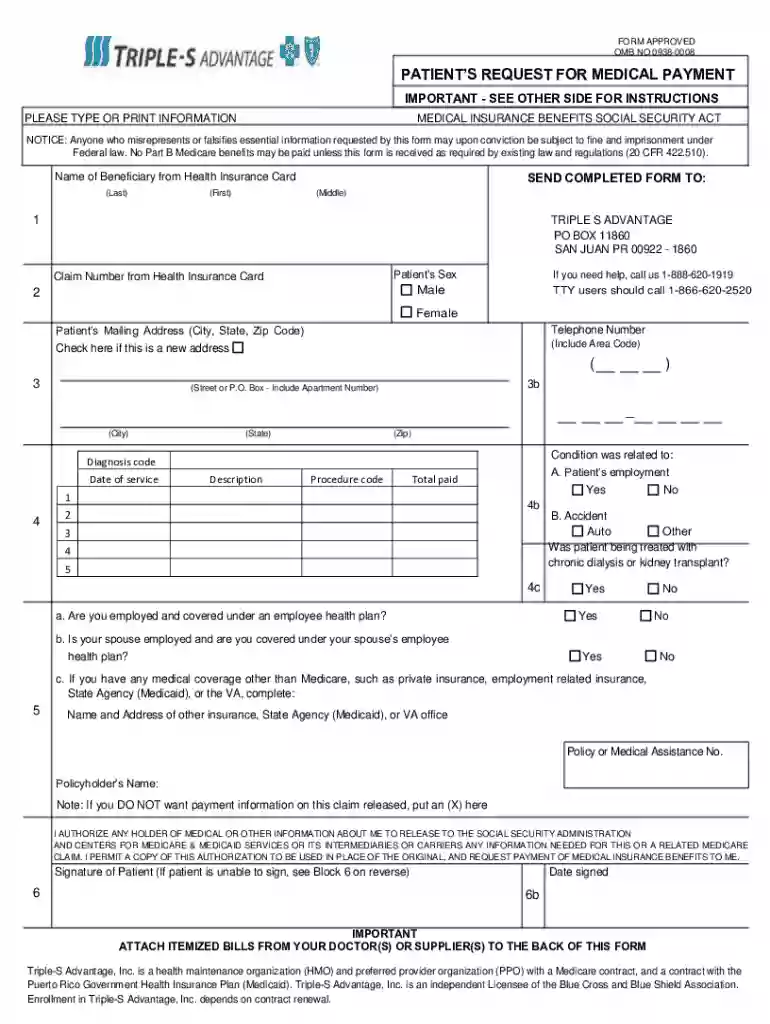
The Patient's Request for Medical Payment form is an essential Medicare document that allows patients to request reimbursement for medical expenses incurred. It facilitates the process for individuals to claim payment for services they have paid for out-of-pocket, ensuring that the Medicare system accurately acknowledges these expenses. This form is particularly relevant for those who experience difficulties with medical billing or discrepancies in service charges.
To effectively use the Patient's Request for Medical Payment, follow these structured steps:
Collect Necessary Information: Before filling out the form, gather all relevant personal and insurance details, invoices, and proof of payment documentation. This ensures you have everything you need to complete the form accurately.
Accurate Form Completion: Carefully enter both personal details and information about the medical services provided. This includes date of service, provider details, and the amount paid.
Attach Required Documentation: Attach copies of all necessary documents, such as invoices and receipts, to substantiate the claim.
Submit the Completed Form: The form and accompanying documents should be submitted according to the specific instructions provided, usually by mail to Triple-S Advantage in Puerto Rico or as otherwise directed by your Medicare provider.
Follow-up: After submission, it's crucial to track the status of your request to ensure it is processed and to address any additional inquiries from Medicare.
Completing the form involves several precise steps:
Personal Information Section: Enter your full name, Medicare number, and contact information as requested.
Medical Service Details: Specify the nature of the medical service received, including the date and the provider's name and address.
Expense Details: Provide an itemized list of services with respective costs. This section must match the invoiced amounts to avoid discrepancies.
Signature and Date: Sign and date the form, confirming the authenticity of the information provided.
Review and Submission: Double-check all filled sections for completeness and accuracy before submitting.
The form incorporates several crucial components:
To complete the process, the following documents are typically required:
This form is primarily used by Medicare beneficiaries who need to claim reimbursements for out-of-pocket expenses when:

When using this form, legal compliance is paramount:
Understanding these terms can assist in completing the form accurately:
These sections ensure comprehensive coverage of the form's purpose, usage, and related processes, enhancing understanding and application in real-world scenarios.
We've got more versions of the Patient s Request For Medical Payment form. Select the right Patient s Request For Medical Payment version from the list and start editing it straight away!
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.