Request To Amend Information On A Form WC-14 WC-14a Preview on Page 1

Request To Amend Information On A Form WC-14 WC-14a 2026

Here's how it works

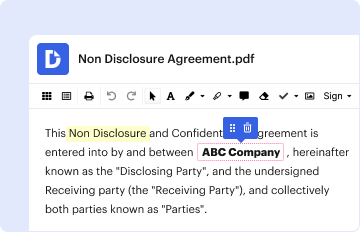
  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

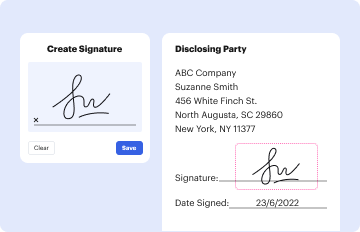
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
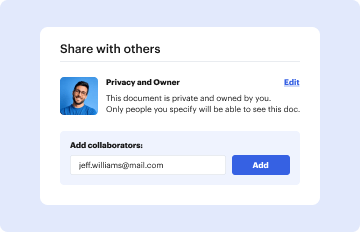
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out Request To Amend Information On A Form WC-14 WC-14a

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by filling in the Board Claim Number at the top of the form. This is essential for tracking your request.
  3. In the EMPLOYEE section, enter the employee's last name, first name, middle initial, birthdate, and mailing address. Ensure accuracy as this information is critical.
  4. Next, provide details about the INSURER/SELF-INSURER including their mailing address and claims office information.
  5. In section A (CLAIM INFORMATION), include the date of injury and employee email. This helps in verifying claim details.
  6. Proceed to section B (INFORMATION TO BE AMENDED) where you can specify what needs to be amended such as date of injury or employer’s name. Check the appropriate boxes and provide any necessary corrections.
  7. Complete section C (AFFIRMATION OF FILING PARTY) by attesting that all provided information is true. Your signature and date are required here.
  8. Finally, fill out section E (CERTIFICATE OF SERVICE) confirming that copies have been sent to all relevant parties and include your contact information.

Start using our platform today to easily complete your Request To Amend Information On A Form WC-14 WC-14a for free!

See more Request To Amend Information On A Form WC-14 WC-14a versions

We've got more versions of the Request To Amend Information On A Form WC-14 WC-14a form. Select the right Request To Amend Information On A Form WC-14 WC-14a version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20184.5 Satisfied (22 Votes)
20074 Satisfied (47 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

The Two Factors That Determine Workers Compensation Claims Whether you are an active employee with your company. Whether your injury occurred as a result of your employment with the company.
The WC-14 form is the official Georgia workers compensation form for filing a claim. Its full title is the Notice of Claim/Request for Hearing/Request for Mediation.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Workers Compensation

While not an amendment before the claimant filed the request at issue.14 provides a two-year statute of limitations for a claimant to seek additional workers

Learn more
WC-14a REQUEST TO CHANGE INFORMATION ON A

CONTACT THE STATE BOARD OF WORKERS COMPENSATION AT 404-656-3818 OR 1-800-533-0682

Learn more
POWER WAVE 455

Whenever you request replacement parts for or information on this equipment 216-383-2211. FAX this completed form to: 216-361-5901.

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here