




Here's how it works
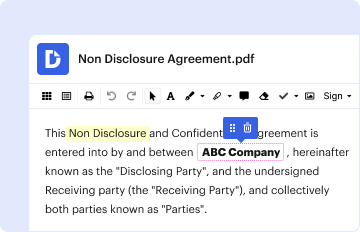
01. Edit your annual premium reimbursement request download online
Type text, add images, blackout confidential details, add comments, highlights and more.
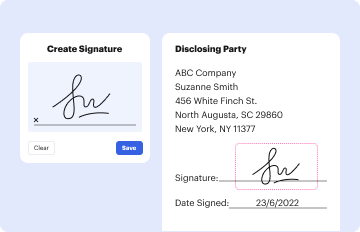
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
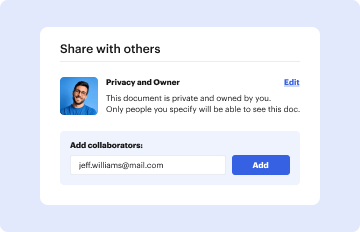
03. Share your form with others
Send annual premium reimbursement request form download via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Medicare Part B Annual Premium Reimbursement Request - un.org with our platform

- Click ‘Get Form’ to open it in the editor.
- In Section 1, clearly print your name, index number, mailing address, retiree number, personal email address, and telephone number. Ensure all information is accurate for processing.
- Move to Section 2 to claim your Part B premiums. Enter the name of the participant, their relationship to you, Medicare ID number, coverage period (from and to), and the monthly premium paid. Remember to attach proof of payment like Form CMS-500.
- If this is your first reimbursement claim, complete Section 3 with your bank information. Provide the bank name, account number, and routing or ABA #. If claiming for a spouse, ensure you use the primary subscriber’s account details.
- Finally, sign and date the form at the bottom to confirm your understanding of ongoing payments for Medicare Part B coverage.
Start using our platform today for free to streamline your Medicare reimbursement process!
Fill out Medicare Part B Annual Premium Reimbursement Request - un.org online
It's free
It's free
See more Medicare Part B Annual Premium Reimbursement Request - un.org versions
We've got more versions of the Medicare Part B Annual Premium Reimbursement Request - un.org form. Select the right Medicare Part B Annual Premium Reimbursement Request - un.org version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more




