signature regarding rights to medical support payments Preview on Page 1

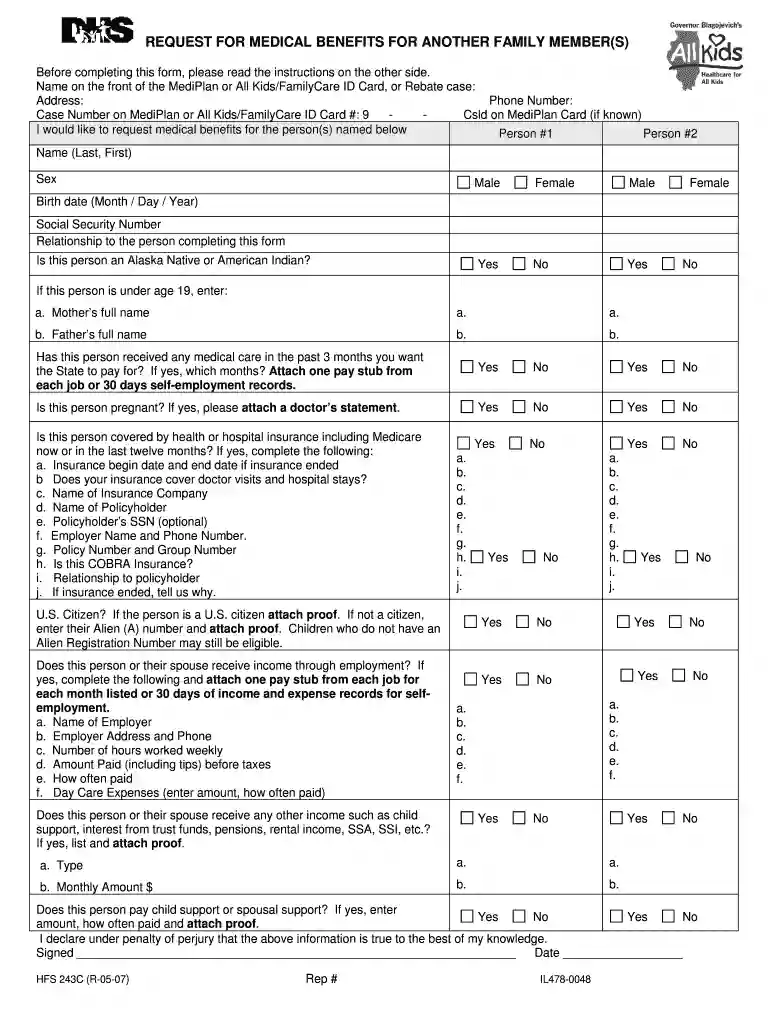
Request for medical benefits for another family member(s) - dhs state il 2026

Here's how it works

  • 01. Edit your signature regarding rights to medical support payments online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send signature on the rights to medical support payments via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out Request for medical benefits for another family member(s) - dhs state il

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by entering your name as it appears on the MediPlan or All Kids/FamilyCare ID Card, along with your address and phone number.
  3. Fill in the case number from your MediPlan or All Kids/FamilyCare ID Card. If known, include the CSID on the MediPlan card.
  4. List the names of the individuals you are requesting benefits for, including their sex, birth date, and Social Security Number.
  5. Indicate your relationship to each person and whether they are an Alaska Native or American Indian. For those under 19, provide parental names.
  6. Answer questions regarding previous medical care received in the last three months and any current insurance coverage details.
  7. Complete income-related sections if applicable, providing necessary documentation such as pay stubs or proof of other income sources.
  8. Finally, review all entered information for accuracy before signing and dating the form at the bottom.

Start using our platform today to easily complete your Request for medical benefits form online for free!

See more signature regarding rights to medical support payments versions

We've got more versions of the signature regarding rights to medical support payments form. Select the right signature regarding rights to medical support payments version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20144.6 Satisfied (28 Votes)
20104 Satisfied (53 Votes)
20074.8 Satisfied (43 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Add a Family Member | HFS

If you want to add another family member to your case, fill out a Request for Medical Benefits for Another Family Member HFS 243C form (pdf) and send it toRead more

Learn more
Illinois Medicaid Redetermination

You may have to re-apply for coverage. You may also need to re-apply for yourself or other family members. To re-apply, visit abe.illinois.gov/access/ orRead more

Learn more
Nanotechnology White Paper

This document has been reviewed in accordance with U.S. Environmental Protection Agency policy and approved for publication and distribution.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here