



01. Edit your bcbs vision claim form online
Type text, add images, blackout confidential details, add comments, highlights and more.

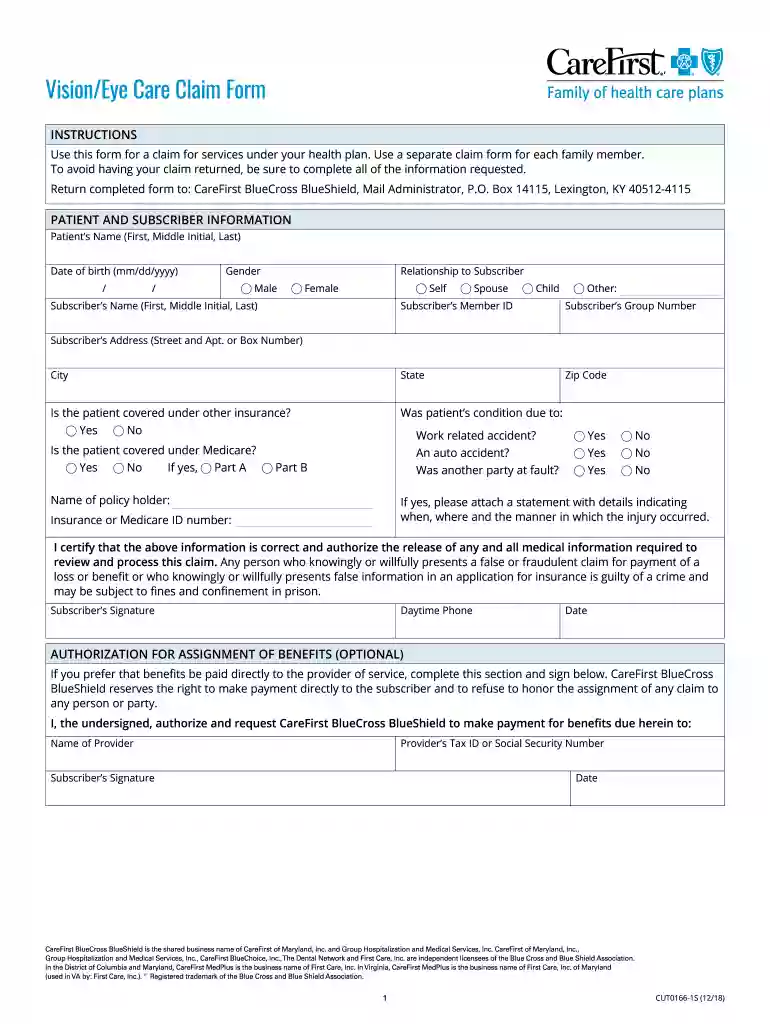
Type text, add images, blackout confidential details, add comments, highlights and more.

Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

Send eye claim form via email, link, or fax. You can also download it, export it or print it out.

Start filling out your vision care claim form today using our platform for free!
We've got more versions of the bcbs vision claim form form. Select the right bcbs vision claim form version from the list and start editing it straight away!
Upload your vision care claim form to DocHub (once you’ve created an account for this). If you need to fill out fields in it, use proper tools from the top pane. For example, add Signature Fields, assign each to a particular person, and click on Sign → Request signatures from others. Personalize your message for your recipients and click Send Request. You can also send your form by fax or as a Signing link instead of using email (you’ll locate these options by navigating to the Menu → Send)
If you are searching for a state-specific carefirst vision claim sample, you can find it in our DocHub Forms & Templates catalog. Use the search field, enter your form’s name, and search through the results for your state. You can also filter out irrelevant results while exploring our catalog by groups.
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
The Health Insurance Claim Form (CMS-1500) is used to bill ophthalmological services and eye appliances to the Medi-Cal program. Because Medi-Cal does notRead more
Oct 1, 2010 Written documentation must be submitted with the paper claim form for two pairs of The vision care provider must submit, with the paper claimRead more
To receive our Vision Care Plan reimbursement, please complete the lower portion of this claim form and attach the entire form,.Read more


