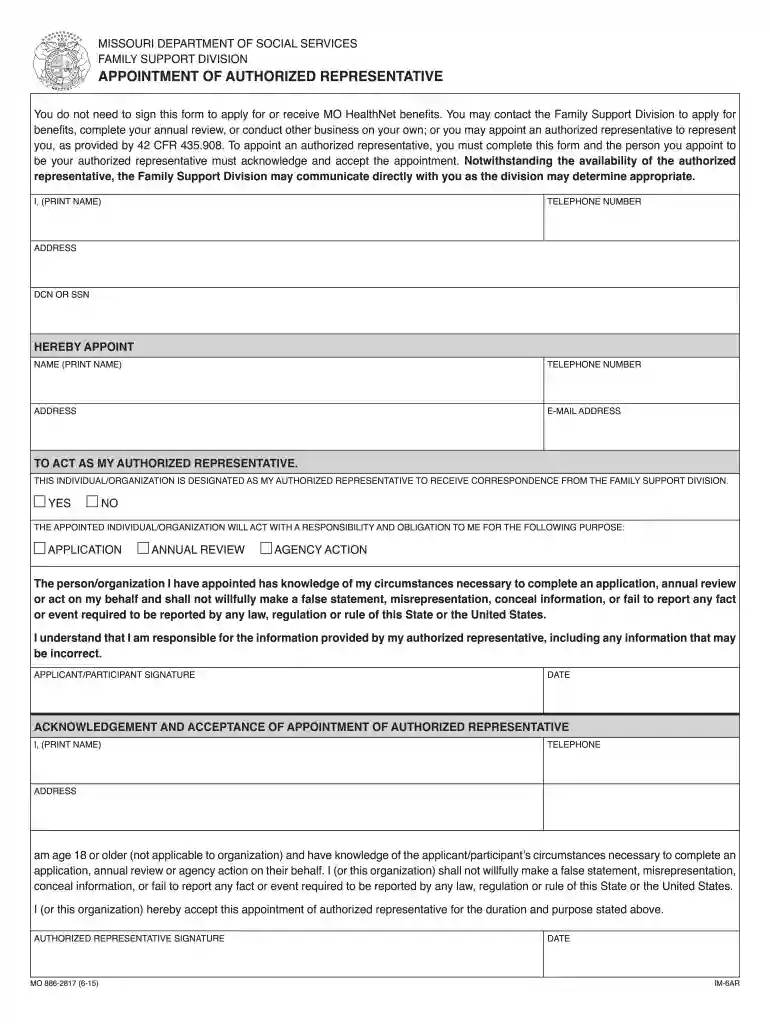
missouri authorized representative form Preview on Page 1

Missouri medicaid authorized representative form 2026

Here's how it works

  • 01. Edit your missouri authorized representative form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send medicaid authorized representative form via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out Missouri Medicaid Authorized Representative Form

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by entering your name, telephone number, address, and either your DCN or SSN in the designated fields at the top of the form.
  3. Next, provide the name, telephone number, and address of the individual or organization you are appointing as your authorized representative.
  4. Indicate the purpose for which you are appointing this representative by checking one of the options: Application, Annual Review, or Agency Action.
  5. Sign and date the form to confirm your appointment of the authorized representative. Ensure that they also sign and date in their section to acknowledge acceptance.

Start using our platform today to easily complete your Missouri Medicaid Authorized Representative Form for free!

See more missouri authorized representative form versions

We've got more versions of the missouri authorized representative form form. Select the right missouri authorized representative form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20244.9 Satisfied (42 Votes)
20154 Satisfied (45 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

missouri medicaid authorized representative form

Appointing an Authorized Representative - DSS Manuals

Fill out this form if you want to name someone or an organization to help you apply for MO HealthNet (MHN),. Temporary Assistance (TA), Supplemental Nutrition.Read more

Learn more
Hospice Provider Manual - 9/1/2023

The patient, patients family or authorized representative may apply for MO Health Net Medicare election form indicating the original election dateRead more

Learn more
NEW YORK STATE MEDICAID PROGRAM DURABLE

Jul 19, 2005 Enter the date on which the provider or an authorized representative signed the claim form. The date should be in the format MM/DD/YY. NoteRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here