



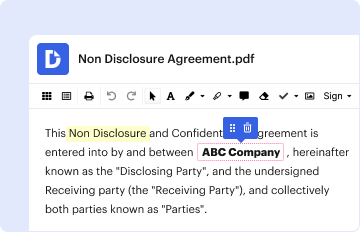
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.


Type text, add images, blackout confidential details, add comments, highlights and more.
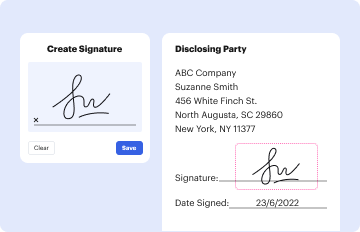
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
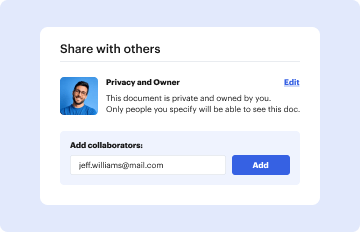
Send it via email, link, or fax. You can also download it, export it or print it out.
The "Consent to Use and Disclose Protected Health Information form" is a legal document that grants permission for healthcare entities to access and share a patient's protected health information (PHI). This consent is vital for enabling healthcare providers to coordinate care, conduct research, and manage billing and insurance processes legally. It often outlines conditions under which specific data can be shared, aligning with regulations such as HIPAA in the United States. These entries ensure protection and outline the patient's rights to confidentiality and data security.
Review Context and Purpose:
Modify According to Needs:
Sign and Date:
Request from Your Healthcare Provider:
Download from Official Websites:
In-Person at Medical Offices:
Fill Personal and Contact Information:
Detail Information to be Disclosed:
Define Purpose of Use/Disclosure:
Identify Recipients:
Form Validation:
Consent Revocation Information:
Patient Control:
Scope of Information:
Disclosure Recipients:
Expiration Date:
Patient Rights:
Compliance with Regulations:
Documentation for Disputes:
Healthcare Providers:
Patients:
Researchers:

We've got more versions of the Consent to Use and Disclose Protected Health Information form form. Select the right Consent to Use and Disclose Protected Health Information form version from the list and start editing it straight away!
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Please read this entire form before signing and complete all the sections that apply to your decisions relating to the disclosure of protected healthRead more
Use these forms to grant permission for others to access your protected health information or request a change to your health record.Read more


