




Here's how it works
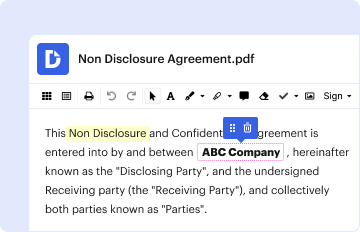
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
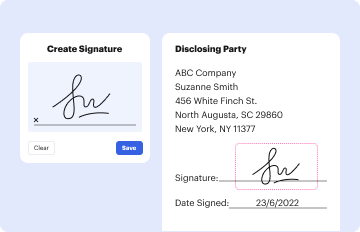
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
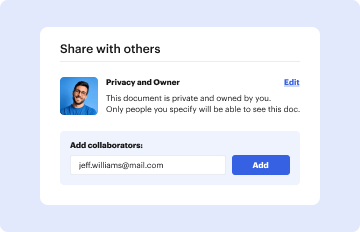
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Hospital Claim Formexisting 20190404

- Click ‘Get Form’ to open it in the editor.
- Begin with Part I, where the patient or their legal guardian must fill in the mandatory fields. Start by entering the Patient’s Membership Number in BLOCK letters.
- Next, provide the Name of Employer if applicable, followed by the Subscriber/Employee's name and the Patient's name if different. Ensure names are formatted correctly with spaces between words.
- Fill in the Occupation field if relevant, and then specify the Date of Hospitalisation or Day Case Surgery.
- If hospitalisation was due to illness, describe symptoms leading to hospitalisation and include dates when symptoms appeared.
- For accidents, provide details such as date, time, place of the accident, and a description of how it happened along with injury specifics.
- Complete any additional sections regarding previous consultations and ensure all required signatures are provided at the end of the form.
Start using our platform today for free to streamline your claim process!
Fill out Hospital Claim Formexisting 20190404 online
It's free
It's free
See more Hospital Claim Formexisting 20190404 versions
We've got more versions of the Hospital Claim Formexisting 20190404 form. Select the right Hospital Claim Formexisting 20190404 version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Release letter - Radical Forgiveness
The document is a Release Letter in which the author grants permission to their spiritually intelligent self to release ...

4-961 Petition for order of protection from domestic abuse Family - nmsupremecourt nmcourts
4-961 Petition for order of protection from domestic abuse Family - nmsupremecourt nmcourts
The document is a petition for an order of protection from domestic abuse under the Family Violence Protection Act in Ne ...

Utah Transfer on Death Deed Form
The document outlines the form and requirements for creating a revocable transfer on death deed in Utah, allowing indivi ...

Maine Health Care Sector Grant Workforce Trainee Application
The Maine Health Care Sector Grant Workforce Trainee Application is designed for unemployed, dislocated, or low-wage wor ...

Employee Performance Evaluation Form - Fairbanks North Star - co fairbanks ak
The document is an Employee Performance Evaluation form for the Fairbanks North Star Borough, designed to assess employe ...

Naperville Central High School - naperville203
The document is a Schedule Change Request Form for Naperville Central High School, allowing students to request changes ...

K:MonicaRace and Ethnicity FINAL report wpd - Census Bureau - census
The document is a comprehensive report on the Census 2000 Testing, Experimentation, and Evaluation Program, focusing on ...

Utilities, Wisconsin - Census Bureau - census
The document is the 1997 Economic Census report for the Utilities sector in Wisconsin, issued by the U.S. Census Bureau. ...


