Authorization for Release of Medical and/or Ophthalmic Records Please complete the following information: Patient 's Name Date of Birth Address City, State, Zip I request and authorize to release all Medical and/or Ophthalmic records of the Preview on Page 1

Authorization for Release of Medical and/or Ophthalmic Records Please complete the following information: Patient 's Name Date of Birth Address City, State, Zip I request and authorize to release all Medical and/or Ophthalmic records of the 2026

Here's how it works

  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

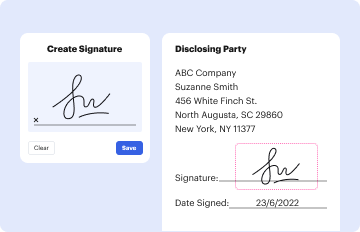
    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

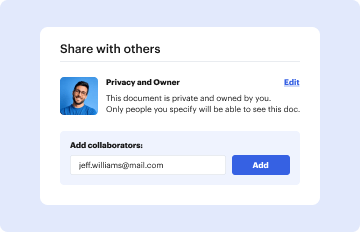
    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out Authorization for Release of Medical and/or Ophthalmic Records

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by entering the Patient's Name in the designated field. Ensure that you spell the name correctly for accurate record-keeping.
  3. Next, input the Date of Birth. This is crucial for identifying the correct medical records associated with the patient.
  4. Fill in the Address, including street, city, state, and zip code. This information helps in verifying the patient's identity.
  5. In the section requesting authorization, specify who is authorized to release the records. For example, write 'English Rows Eye Care' as indicated.
  6. Review and check all items listed under what is included in this request. Make sure all necessary documents are covered.
  7. Sign and date at the bottom of the form to validate your authorization. If someone else is signing on behalf of the patient, complete their information as a guardian or representative.

Start using our platform today to easily fill out your Authorization for Release of Medical and/or Ophthalmic Records for free!

See more Authorization for Release of Medical and/or Ophthalmic Records Please complete the following information: Patient 's Name Date of Birth Address City, State, Zip I request and authorize to release all Medical and/or Ophthalmic records of the versions

We've got more versions of the Authorization for Release of Medical and/or Ophthalmic Records Please complete the following information: Patient 's Name Date of Birth Address City, State, Zip I request and authorize to release all Medical and/or Ophthalmic records of the form. Select the right Authorization for Release of Medical and/or Ophthalmic Records Please complete the following information: Patient 's Name Date of Birth Address City, State, Zip I request and authorize to release all Medical and/or Ophthalmic records of the version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20094.6 Satisfied (53 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

request for and authorization to release health information

LAST NAME- FIRST NAME- MIDDLE NAME. DATE OF BIRTH (MM/DD/YYYY). PATIENTS MAILING ADDRESS (including City, State and Zip Code). NAME AND ADDRESS OFRead more

Learn more
of 3 The Eye Care Institute Authorization for Use or Disclosure

I authorize release/disclosure of the patients health records and information: Entire Medical Record Medical Record for Specific Date of Service

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here