




Here's how it works
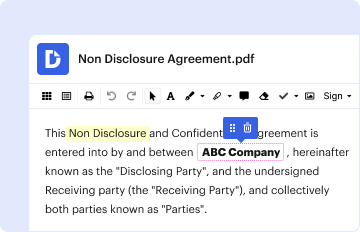
01. Edit your facebook marketplace appeal form pdf online
Type text, add images, blackout confidential details, add comments, highlights and more.
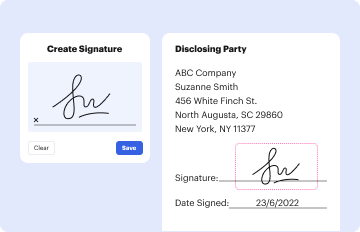
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
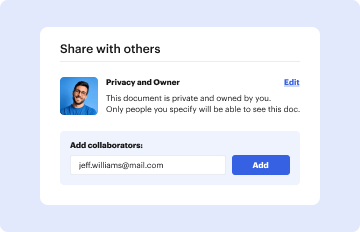
03. Share your form with others
Send facebook marketplace appeal form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Marketplace Appeal Request Form D - Affordable Health Insurance with our platform

- Click ‘Get Form’ to open it in the editor.
- Begin by filling out the 'APPELLANT 1' section. Enter your first name, middle name, last name, date of birth, phone number, email address, and complete address details.
- List any other household members who are also filing an appeal in the designated area. If there are more than four appellants, attach a separate sheet with their names.
- In the 'Reasons for filing an appeal' section, clearly explain why you believe there was a mistake regarding eligibility. Be specific about the issues such as income or household size.
- If applicable, provide information for an authorized representative who will assist you in this process. Fill out their contact details accurately.
- Review all entered information for accuracy before signing at the bottom of the form. Ensure that all adults in your household have signed where required.
Start using our platform today to easily fill out and submit your Marketplace Appeal Request Form D for free!
Fill out Marketplace Appeal Request Form D - Affordable Health Insurance ... online
It's free
It's free
See more Marketplace Appeal Request Form D - Affordable Health Insurance ... versions
We've got more versions of the Marketplace Appeal Request Form D - Affordable Health Insurance ... form. Select the right Marketplace Appeal Request Form D - Affordable Health Insurance ... version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more




