




Here's how it works
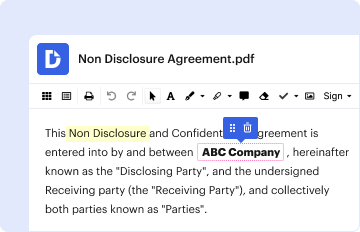
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
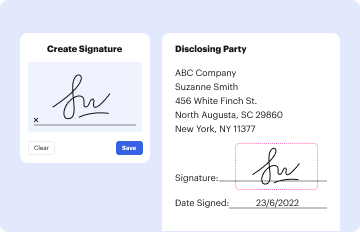
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
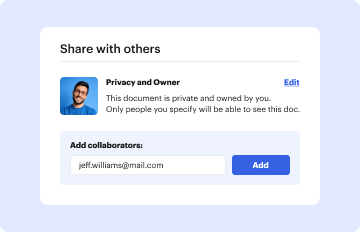
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Authorization for release of Medical Information - LifeBridge Health with our platform

- Click ‘Get Form’ to open it in the editor.
- Begin by entering the Patient’s Name, Date of Birth, and Street Address in the designated fields. Ensure accuracy as this information is crucial for identification.
- Fill in the Social Security Number, City, State, Zip Code, and Phone Number to provide complete contact details.
- In the authorization section, specify who is authorized to release and obtain medical records by filling in the names and contact information of individuals or agencies.
- Clearly state the purpose for the disclosure in the provided space. This helps clarify why you are requesting this information.
- Select which medical records you wish to be released by checking the appropriate boxes. Be mindful that some records may contain sensitive information.
- Sign and date the form at the bottom. Include your relationship to the patient if applicable.
- If required, have a witness sign and date as well. Review all entries for completeness before submission.
Start using our platform today to easily fill out your Authorization for release of Medical Information!
Fill out Authorization for release of Medical Information ... - LifeBridge Health - lifebridgehealth online
It's free
It's free
See more Authorization for release of Medical Information ... - LifeBridge Health - lifebridgehealth versions
We've got more versions of the Authorization for release of Medical Information ... - LifeBridge Health - lifebridgehealth form. Select the right Authorization for release of Medical Information ... - LifeBridge Health - lifebridgehealth version from the list and start editing it straight away!
Got questions?
We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.
Contact us
What is an example of a HIPAA authorization?
I hereby authorize use or disclosure of protected health information about me as described below. 4. I understand that the information used or disclosed may be subject to re-disclosure by the person or class of persons or facility receiving it, and would then no longer be protected by federal privacy regulations.
How do I give permission to share medical information?
Explicit consent It can be given in writing, verbally or through another form of communication, such as sign language.
How to fill out authorization to release information?
Begin by specifying your name, the entity authorized to disclose information, and the individuals or entities you authorize to receive it. Indicate the specific information and purpose for which it will be disclosed, add an expiration date or event, and sign and date the form to confirm your consent.
How to fill out authorization for release and use of medical information?
0:43 1:58 A description of the protected. Health information to be used and disclosed. The person authorizedMoreA description of the protected. Health information to be used and disclosed. The person authorized to make the use or disclosure. The person to whom the covered entity may make the disclosure.
Do you authorize the release of medical information?
Your health information cannot be used or shared without your written permission unless this law allows it. For example, without your authorization, your provider generally cannot: Give your information to your employer. Use or share your information for marketing or advertising purposes or sell your information.
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


People also ask
What is an authorization letter for medical purposes on my behalf?
How to Write a Medical Authorization Letter. Begin with your full name, address, and contact information, followed by the current date. These details identify the author of the letter. Clearly mention the name and relationship of the person or organization being authorized to act on your behalf.
How do you write an authorization letter for medical records release?
I, the undersigned, authorize the release of, or request access to the information specified below from the medical record(s) of the above name patient. I understand that my records are confidential and cannot be disclosed without my written authorization, except when otherwise permitted by law.
What are the 8 requirements of a valid authorization to release information?
8 Key Elements of a Compliant Medical Records Release Form Patient Information. Purpose of Request. Dates of Service. Recipient Information. Valid Authorization Signature. Date of Signature. Restrictions or Limitations. Revocation Clause.