




Here's how it works
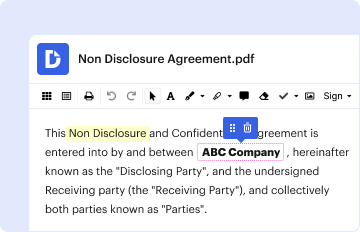
01. Edit your fair hearing status approved defend online
Type text, add images, blackout confidential details, add comments, highlights and more.
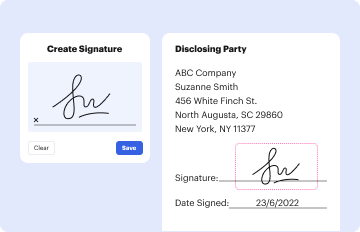
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send disabilityrightsca via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Fair Hearing Request Form 1-01 with our platform

- Click ‘Get Form’ to open it in the editor.
- Begin by entering the name of the person for whom the hearing is requested (the claimant) along with their date of birth.
- Indicate whether the claimant is a Medicaid Home and Community Based Services Waiver participant by checking 'Yes' or 'No'.
- Fill in the address and daytime telephone number of the claimant.
- Specify the name of the regional center or state developmental center involved.
- If you wish to resolve matters before a fair hearing, check any applicable options for an informal meeting or mediation.
- Clearly describe your reasons for requesting a fair hearing and what is needed to resolve your complaint.
- If you are not the claimant, provide your name, relationship to the claimant, and contact information.
- Sign and date the request form, ensuring all required fields are completed accurately.
- If necessary, indicate if interpreter services are required and specify the language needed.
Start filling out your Fair Hearing Request Form 1-01 today for free using our platform!
Fill out Fair Hearing Request Form 1-01. Fair Hearing Request Form 1-01 - disabilityrightsca online
It's free
It's free
See more Fair Hearing Request Form 1-01. Fair Hearing Request Form 1-01 - disabilityrightsca versions
We've got more versions of the Fair Hearing Request Form 1-01. Fair Hearing Request Form 1-01 - disabilityrightsca form. Select the right Fair Hearing Request Form 1-01. Fair Hearing Request Form 1-01 - disabilityrightsca version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more




