




Here's how it works
01. Edit your pharmanet login online
Type text, add images, blackout confidential details, add comments, highlights and more.
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send hlth 5551 via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out pharmanet patient with our platform

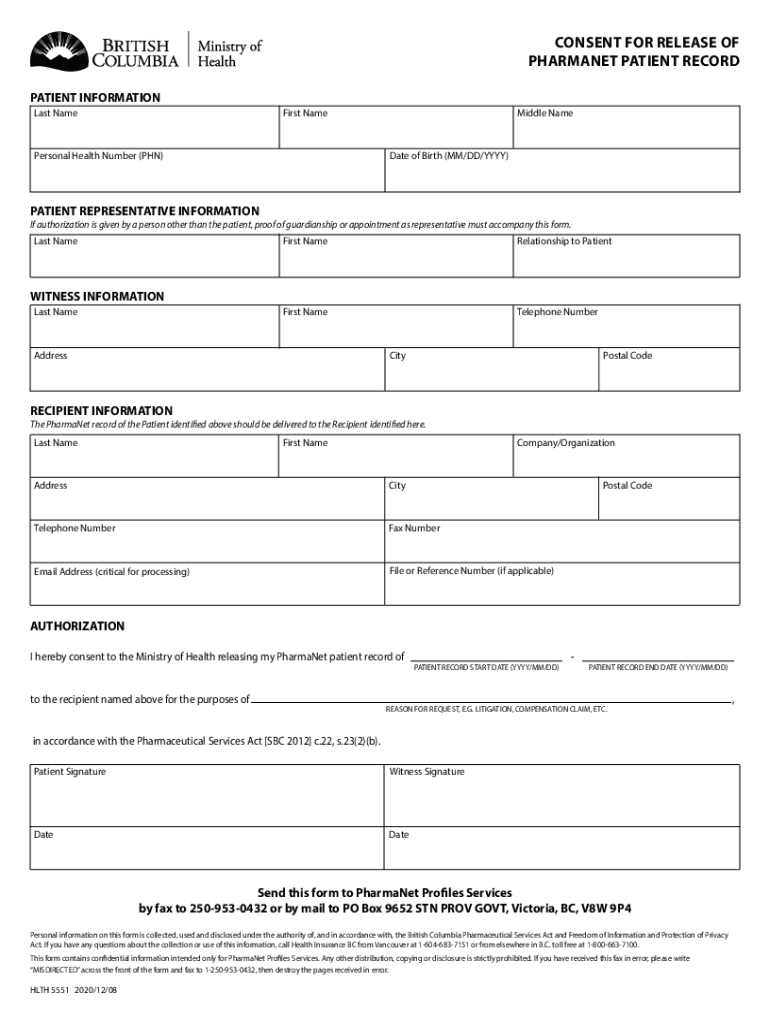
- Click ‘Get Form’ to open the pharmanet patient document in the editor.
- Begin by filling out the Patient Information section. Enter the Last Name, First Name, Middle Name, Personal Health Number (PHN), and Date of Birth in the specified fields.
- If applicable, complete the Patient Representative Information section. Provide the representative's Last Name, First Name, Relationship to Patient, and Telephone Number.
- Next, fill in the Witness Information. Include the Witness's Last Name, Address, City, and Postal Code.
- In the Recipient Information section, enter details for where the PharmaNet record should be sent. This includes Last Name, First Name, Company/Organization, Address, City, Telephone Number, Fax Number, Email Address (critical for processing), File or Reference Number (if applicable), and Postal Code.
- Complete the Authorization section by consenting to release your PharmaNet patient record. Specify the Patient Record Start Date and End Date along with the Reason for Request.
- Finally, sign and date both Patient Signature and Witness Signature fields before submitting your form via fax or mail as instructed.
Start using our platform today to easily fill out your pharmanet patient form online for free!
Fill out pharmanet patient online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


