




Here's how it works
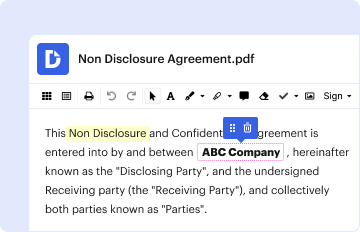
01. Edit your aptp form online
Type text, add images, blackout confidential details, add comments, highlights and more.
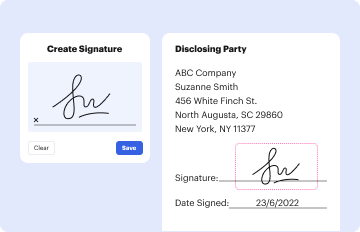
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
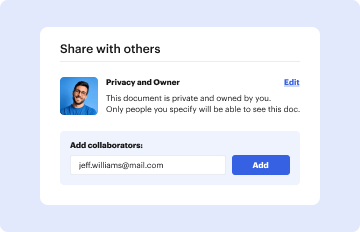
03. Share your form with others
Send nj aptp form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out aptp form with our platform

- Click ‘Get Form’ to open the aptp form in the editor.
- Begin by filling out the 'Patient Information' section. Enter the patient's name, address, city, state, and telephone number. Ensure all details are accurate for effective processing.
- Next, provide the 'Policyholder Information' if it differs from the patient. Include their name, address, and relationship to the patient.
- In the 'Provider Information' section, input the treating provider's name, specialty, and contact details. This information is crucial for communication regarding treatment.
- Complete the 'Patient Medical History' by checking applicable services received by the patient. Remember to attach a brief description of each service on a separate document.
- Finally, review all entries for accuracy before signing and dating the form at the bottom. This ensures that your submission is complete and correct.
Start using our platform today to easily fill out your aptp form online for free!
Fill out aptp form online
It's free
It's free
See more aptp form versions
We've got more versions of the aptp form form. Select the right aptp form version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2004 | 4.9 Satisfied (324 Votes) |
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Skidmore v Led Zeppelin - Ninth Circuit Court of Appeals
The document is a supplemental reply brief filed by Kathryn Marie Jones in her appeal against Medtronic in the United St ...

DEPARTMENT OF CITY AND REGIONAL PLANNING: AY
The document is a declaration form for students in the Department of City and Regional Planning to complete as part of t ...

SERVICES AGREEMENT To initiate a new project matter
The document is an intake form from Clemson University's Office of Industry Contracts, designed to initiate new projects ...

Accelerated Bachelor's Graduate Study Plan Authorization
The document outlines the guidelines and application process for the Accelerated Bachelor's/Graduate Study Plan (G-ABGSP ...
UH Status Verification docx
The document outlines the verification process for University of Hawaii (UH) affiliation, detailing required information ...

LVC Growing Equestrian Application
The Growing Equestrians Scholarship, offered by Lodi Veterinary Care, aims to support young individuals (21 years or you ...

INSTRUCTIONS FOR COMPLETION OF SUMMER CAMP PACKET
The document provides detailed instructions for completing the Summer Camp Packet for Colonial Sports, including registr ...

2019 Drexel University Verification Checklist
The document is a 2020–2021 Verification Checklist for students whose FAFSA was selected for verification by Drexel Univ ...


